

ENT (Ear, Nose and Throat) · Jaipur Hospital
Allergic Rhinitis Management in Jaipur
Constant sneezing and blocked nose? Get a clear diagnosis and a step-by-step treatment plan.
- Serving Jaipur since 1991 (35 years)
- NABH accredited
- 24×7 emergency & ICU
- Cashless: RGHS, MAA Yojana, CGHS + 22 insurers
- Treatment length
- Ongoing (3 to 5 years for immunotherapy)
- Anaesthesia
- Not needed
- Recovery
- Symptom control in 2 to 4 weeks
- Price
- ₹2,000 to ₹15,000 per year (immunotherapy ₹50,000 to ₹1,00,000 full course)typical range in India; ask us for an estimate
Nasal allergies disrupt daily life
Sneezing, congestion and itchy eyes that won't go away
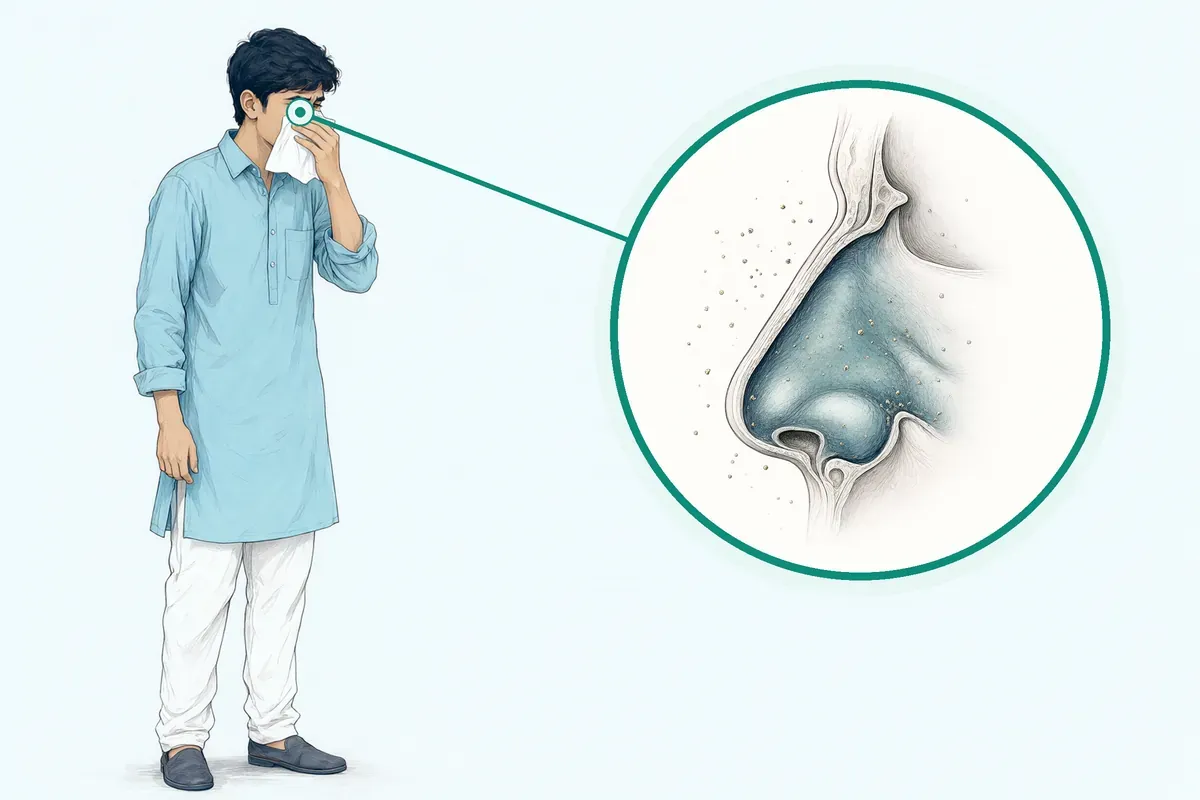
Allergic rhinitis affects 20% to 30% of people in India and often links with asthma. Symptoms disturb sleep, work and school, and many patients feel tired and unable to concentrate.
-
Sleep and focus suffer
Nasal blockage at night leads to poor sleep, daytime fatigue and trouble concentrating at work or school.
-
Medicines only mask symptoms
Sprays and tablets help for a while but do not change the underlying allergy; symptoms return when you stop.
-
Triggers are hard to avoid
Dust mites, pollen and pollution in Jaipur make complete avoidance nearly impossible for most families.
-
Risk of asthma later
About 15% of people with allergic rhinitis in India go on to develop asthma if the allergy is not managed.
Allergic rhinitis is an IgE-mediated inflammatory disease of the nasal mucosa triggered by inhaled allergens.
Why Jaipur Hospital
You worry that the constant sneezing and blocked nose will never let you sleep properly or focus at work, and you do not want to rely on sprays forever.
Your care plan
Your first steps with us
- 1 Call or visit OPD for ENT consultation
- 2 Get allergy testing and nasal examination done in-house
- 3 Start personalised medical plan or immunotherapy schedule
- 4 Attend regular follow-ups to adjust treatment and track progress
how the treatment is planned
Your ENT surgeon takes a detailed history, examines the nose and may order skin prick or blood tests to identify triggers. Treatment is then matched to your symptom pattern and severity.
-
Intranasal Corticosteroids
Daily spray to reduce nasal inflammation; first-line for persistent or moderate-to-severe symptoms.
-
Antihistamines
Oral or nasal spray for sneezing and runny nose; second-generation types cause less drowsiness.
-
Sublingual Immunotherapy (SLIT)
Allergen drops under the tongue at home for long-term desensitisation; suitable for selected patients.
-
Subcutaneous Immunotherapy (SCIT)
Allergy shots given in clinic over 3 to 5 years for severe or multi-allergen cases; requires observation after each dose.
Why patients trust us
- 1991 Serving Jaipur for 35 years
- NABH Accredited hospital
- 2 ENT (Ear, Nose and Throat) consultants
- 24×7 Emergency, ICU and ambulance
- 25 Cashless schemes and insurers
what research shows about this treatment
-
3 to 5 years
Immunotherapy courses typically run for three to five years to achieve lasting benefit after stopping.
-
significant reduction of symptoms and/or drug intake scores
Most controlled trials of local nasal immunotherapy documented meaningful symptom relief and less medication use.
-
20%–30% prevalence in India
Population studies estimate that two to three in ten people in India have allergic rhinitis.
If it is left untreated
Untreated allergic rhinitis can worsen sleep, reduce work and school productivity, and is linked to developing asthma, sinusitis and ear infections over time.
life after treatment
Most people find their nasal symptoms become manageable, sleep improves and they need fewer daily medicines.
-
Fewer bad days
Sneezing and congestion become occasional rather than daily, so you can plan activities without worry.
-
Better sleep and energy
Nasal breathing improves at night, leading to less fatigue and better concentration next day.
-
Less medicine needed
With immunotherapy, many patients reduce or stop daily sprays and tablets after the build-up phase.
-
Lower asthma risk
Controlling nasal allergy early may reduce the chance of developing allergic asthma later.


Frequently asked questions
Questions patients ask about allergic rhinitis management
What is allergic rhinitis management?
In short
Allergic rhinitis management at Jaipur Hospital means controlling nasal allergy symptoms through medicines, allergen avoidance and immunotherapy. It is an outpatient plan that aims to reduce sneezing, runny nose, congestion and itching. Treatment length is ongoing, with immunotherapy lasting three to five years.
In detail
Allergic rhinitis is an IgE-mediated inflammatory disease of the nasal mucosa. The ARIA guidelines classify it as intermittent or persistent and mild or moderate-to-severe. First-line pharmacotherapy is intranasal corticosteroids for persistent disease. Second-generation antihistamines help with sneezing and itching.
Combination sprays may be used when monotherapy is insufficient. Allergen immunotherapy (sublingual or subcutaneous) is the only disease-modifying option and is offered when symptoms remain uncontrolled despite medicines and avoidance, or when a patient wishes to reduce long-term medication use.
Environmental controls target identified allergens such as dust mites, pollen, mould or pet dander. Saline irrigation is recommended for all patients. Surgery is not a treatment for the allergy itself but may be considered for structural problems like turbinate hypertrophy or polyps.
A common belief
Many people think a single spray or tablet is enough.
What actually happens
In persistent or moderate-to-severe disease, monotherapy often fails and combination therapy or immunotherapy is needed for lasting control.
Your next step at Jaipur Hospital
Your surgeon will assess symptom pattern, severity and impact on daily life. Skin prick testing or blood tests for specific IgE may be done to identify triggers. A personalised plan combining sprays, tablets, avoidance measures and, if suitable, immunotherapy will be discussed. Immunotherapy requires a commitment of three to five years with regular follow-ups.
Which specialist should I see for this problem?
In short
You should see an ENT (otolaryngology) specialist or an allergist at Jaipur Hospital. Our Otolaryngology department evaluates nasal symptoms, performs endoscopic examination and coordinates allergy testing. For immunotherapy, a clinician trained in allergen immunotherapy will supervise the treatment.
In detail
Guidelines recommend referral to an allergist or immunologist for severe or refractory disease, uncertainty about clinically relevant allergens, consideration of allergen immunotherapy, or substantial impairment in quality of life.
Referral to an otolaryngologist is appropriate when structural abnormalities, chronic rhinosinusitis, nasal polyps, recurrent epistaxis or other conditions requiring endoscopic evaluation or surgical management are suspected.
At Jaipur Hospital, the ENT team works with allergy-trained clinicians to provide comprehensive care including skin prick testing, intranasal corticosteroid and antihistamine prescriptions, and both sublingual and subcutaneous immunotherapy.
The choice of specialist depends on whether the primary need is medical management, allergy testing and immunotherapy, or assessment for surgical issues like turbinate hypertrophy or septal deviation.
A common belief
Some patients go only to a general physician or try self-medication for years.
What actually happens
An ENT can assess nasal structure, rule out polyps or sinusitis, and arrange proper allergy testing in one visit.
Your next step at Jaipur Hospital
Start with an ENT consultation at our OPD. The doctor will take a detailed history, examine the nose with an endoscope if needed, and decide if allergy testing or a pulmonology opinion for co-existing asthma is required. Most patients are managed entirely within the ENT and allergy service.
What treatment options are available for my situation?
In short
At Jaipur Hospital, treatment options include intranasal corticosteroids (first-line for persistent symptoms), oral or intranasal antihistamines (for sneezing and runny nose), combination nasal sprays, saline irrigation, leukotriene receptor antagonists (mainly if asthma co-exists), and allergen immunotherapy (sublingual drops or subcutaneous injections) for long-term desensitisation. Avoidance of identified allergens is always advised.
In detail
The ARIA and international guidelines recommend a stepwise approach. Intranasal corticosteroids are the most effective monotherapy for persistent or moderate-to-severe disease. Second-generation antihistamines are preferred for mild or intermittent symptoms. Fixed-dose combination sprays (corticosteroid plus antihistamine) offer greater control for moderate-to-severe cases.
Saline irrigation is suggested for all patients. Short-term decongestants may be used for severe congestion but not beyond a few days to avoid rebound.
Allergen immunotherapy (SLIT or SCIT) is the only disease-modifying treatment and is indicated when symptoms remain inadequately controlled despite pharmacotherapy and avoidance, or when the patient wishes to reduce long-term medication use.
SLIT is given as daily drops under the tongue at home after the first supervised dose. SCIT involves weekly then monthly injections in a clinical setting over three to five years. Both routes are effective for pollen, dust mite and certain animal allergens.
Surgery such as inferior turbinate reduction is only for refractory nasal obstruction due to structural enlargement after medical therapy fails.
A common belief
People often rely only on antihistamines.
What actually happens
For persistent symptoms, nasal steroids are more effective. Immunotherapy is the only treatment that can modify the disease course, but it needs three to five years of commitment.
Your next step at Jaipur Hospital
Your doctor will classify your symptom pattern (sneeze-runner or blocker type), severity and triggers, then recommend a tailored combination. Immunotherapy requires a three to five year commitment with regular follow-ups. Costs range from ₹2,000 to ₹15,000 per year for medicines; a full immunotherapy course typically costs ₹50,000 to ₹1,00,000.
What can I safely do at home to manage allergic rhinitis symptoms?
In short
You can use saline nasal rinses, keep windows closed during high pollen periods, and use allergen-proof bedding covers. Jaipur Hospital advises these measures alongside prescribed treatment. Regular washing of bedding in hot water and maintaining low indoor humidity help reduce dust mite exposure.
In detail
Environmental control measures should target clinically relevant allergens identified through your history and allergy testing. For seasonal allergens, limiting outdoor exposure during high pollen counts, keeping windows closed, using air conditioning, and showering after outdoor activities may help.
For indoor allergens, a comprehensive approach works better than single steps: allergen-impermeable mattress and pillow covers, regular hot-water washing of bedding, and low indoor humidity for dust mites; moisture control for mould; and pet avoidance or HEPA filtration for animal dander.
Avoiding tobacco smoke, strong odours, and rapid temperature changes also helps. Isotonic intranasal saline is suggested for all patients with allergic rhinitis. Adherence to prescribed pharmacotherapy before and during anticipated allergen exposure may prevent symptom exacerbations.
A common belief
Many people try one single fix, like an air purifier alone, and find it does not work.
What actually happens
Evidence shows a combined approach works better for dust mites, and pet removal is the most effective step for animal allergy. Random avoidance without knowing your triggers wastes effort.
Your next step at Jaipur Hospital
Start with the measures that match your identified triggers. Use saline rinses daily if they help. Keep a symptom diary to see what worsens your nose. Review these steps with your doctor at follow-up.
How does the term "hay fever" relate to allergic rhinitis management?
In short
Hay fever is the common name for seasonal allergic rhinitis triggered by pollen. At Jaipur Hospital, our ENT team treats hay fever with the same evidence-based approach used for all allergic rhinitis. Management focuses on identifying your specific triggers, controlling symptoms with medication, and offering immunotherapy when appropriate.
In detail
The term hay fever describes allergic rhinitis that occurs during pollen seasons. Evidence shows that intranasal corticosteroids are the most effective first-line treatment for persistent or moderate-to-severe symptoms. Second-generation antihistamines help with sneezing and itching.
For patients whose symptoms remain inadequately controlled despite pharmacotherapy and allergen avoidance, allergen immunotherapy (sublingual or subcutaneous) may modify the long-term course of the disease. Environmental controls such as keeping windows closed during high pollen counts and showering after outdoor activities can reduce exposure.
A common belief
Many people think hay fever only needs antihistamines.
What actually happens
But guidelines show intranasal corticosteroids are more effective for persistent symptoms, and immunotherapy is the only treatment that can modify the disease long-term.
Your next step at Jaipur Hospital
If you have seasonal nasal symptoms, book a consultation at Jaipur Hospital. Our ENT specialists will take a detailed history, perform an examination, and may recommend allergy testing to confirm your triggers.
A personalised plan usually starts with intranasal corticosteroids and antihistamines, with immunotherapy considered for long-term control. Treatment response is reviewed periodically.
Is the blockage caused by allergy, sinus disease, polyps, or a bent septum?
In short
Nasal blockage can result from allergic rhinitis, chronic sinusitis, nasal polyps, or a deviated septum, and often more than one factor is present. At Jaipur Hospital, our ENT team uses clinical examination and, when needed, nasal endoscopy to determine the exact cause and guide targeted treatment.
In detail
Allergic rhinitis causes blockage through mucosal swelling and inflammation. Chronic rhinosinusitis adds thick secretions and mucosal oedema. Nasal polyps, often associated with allergy, create physical obstruction. A deviated septum narrows the airway structurally. Guidelines recommend against routine sinonasal imaging for uncomplicated allergic rhinitis.
Imaging may be considered when symptoms persist despite optimised medical therapy or when structural abnormalities are suspected. Inferior turbinate reduction may be offered for enlarged turbinates that fail medical management. The clinical history, pattern of symptoms, and endoscopic findings help differentiate these causes.
A common belief
Many patients assume a scan is needed straight away.
What actually happens
Guidelines advise against routine imaging for simple allergic rhinitis. A careful endoscopic examination in the clinic usually identifies the cause and avoids unnecessary radiation.
Your next step at Jaipur Hospital
If you have persistent nasal blockage, book an ENT consultation at Jaipur Hospital. Our specialists will perform a thorough nasal examination, which may include diagnostic nasal endoscopy in the clinic. Based on findings, a treatment plan is started with intranasal corticosteroids and saline irrigation. If structural issues or polyps are identified, further imaging or surgical options will be discussed.
Could the problem affect hearing, balance, breathing, speech, or swallowing?
In short
Allergic rhinitis can affect hearing and breathing, and may influence speech quality, but it does not directly cause balance or swallowing problems. At Jaipur Hospital, our ENT specialists assess the full impact of nasal allergy on the upper airway and related structures.
In detail
Nasal obstruction from allergic rhinitis forces mouth breathing, which can alter speech resonance and cause dry throat. Eustachian tube dysfunction secondary to nasal inflammation may lead to middle ear effusion, causing hearing reduction or a sensation of fullness. This is more common in children.
Balance is not typically affected unless inner ear involvement occurs, which is rare in isolated allergic rhinitis. Swallowing is not directly impaired, though postnasal drip may cause throat clearing or cough. Chronic rhinosinusitis or nasal polyps, which can coexist with allergy, may worsen these effects. Guidelines recommend assessing for associated conditions such as otitis media and sleep-disordered breathing in all patients with allergic rhinitis.
A common belief
Patients often worry about dizziness or choking.
What actually happens
These are not typical features of allergic rhinitis. Hearing changes from middle ear fluid are common and usually reversible with nasal inflammation control.
Your next step at Jaipur Hospital
If you notice hearing changes, persistent mouth breathing, or speech concerns alongside nasal symptoms, book an ENT evaluation at Jaipur Hospital. Our team will examine the ears, nose, and throat, check for middle ear effusion, and assess nasal airflow.
Treatment of the underlying allergic inflammation with intranasal corticosteroids and saline irrigation often improves these secondary effects. Further management of any coexisting conditions will be discussed.
Which symptoms or changes should prompt me to seek medical advice?
In short
Seek medical advice at Jaipur Hospital if you have frequent sneezing, runny or blocked nose, nasal itching, postnasal drip or itchy, watery eyes that affect sleep, work or school. Also consult if over-the-counter medicines do not help, symptoms last more than a few weeks, or you develop wheezing, sinus pain or frequent infections.
In detail
Allergic rhinitis commonly presents with sneezing, anterior rhinorrhoea, nasal congestion, nasal itching and itchy, watery eyes. These symptoms can impair quality of life, causing sleep disturbance, fatigue, irritability and poor concentration.
The ARIA guidelines recommend assessment for associated conditions such as asthma, conjunctivitis, sinusitis, otitis media and sleep-disordered breathing. If symptoms persist despite empiric treatment, or if the diagnosis is uncertain, specific IgE testing is indicated.
Red flags include unilateral symptoms, blood-stained discharge, facial pain, or symptoms that do not respond to standard therapy, which may suggest structural or other pathology requiring ENT evaluation.
A common belief
People often wait years, thinking it is just a cold or seasonal nuisance.
What actually happens
Untreated allergic rhinitis can worsen asthma, cause sinus infections and reduce productivity. Early assessment prevents complications.
Your next step at Jaipur Hospital
Track your symptom pattern and triggers for a week before your visit. Note any seasonal variation, exposure to pets, dust or mould, and response to any medicines tried. Bring a list of current medications. The doctor will take a focused history, examine the nose and may arrange skin prick testing or blood tests.
What will the doctor ask and check at the first visit?
In short
At Jaipur Hospital, the doctor will ask about your symptom pattern, triggers, seasonality, family history of allergy or asthma, current medications and impact on sleep and work. The nose will be examined with a speculum or endoscope to look for pale mucosa, clear discharge, turbinate swelling or polyps.
In detail
Guidelines state the clinical diagnosis of allergic rhinitis is based on history and physical findings consistent with an allergic cause: nasal congestion, runny nose, itchy nose or sneezing. Examination findings include clear rhinorrhoea, nasal congestion, pale discoloration of the nasal mucosa and red, watery eyes.
The doctor will assess for associated conditions such as asthma, atopic dermatitis, conjunctivitis, sinusitis, otitis media and sleep-disordered breathing.
If the diagnosis is uncertain, or if symptoms do not respond to empiric treatment, or if specific allergens need identification for targeted therapy or immunotherapy, specific IgE testing (skin prick or blood test) will be recommended. Routine sinonasal imaging is not recommended for straightforward allergic rhinitis.
A common belief
Patients often expect a scan or blood test immediately.
What actually happens
Guidelines advise against routine imaging. Diagnosis is clinical; testing is added only when needed for immunotherapy planning or unclear cases.
Your next step at Jaipur Hospital
Bring a symptom diary if possible, noting time of day, season, exposures and medicine use. List all current drugs including nasal sprays. The visit takes 20 to 30 minutes. Skin prick testing, if done, gives results in 15 to 20 minutes. A treatment plan is usually discussed the same day.
Can this problem improve without a procedure or operation?
In short
Yes, allergic rhinitis at Jaipur Hospital is primarily managed without surgery. Most patients achieve good symptom control with medicines, allergen avoidance and immunotherapy. Surgery is only considered for structural problems like a deviated septum, large turbinates or polyps that persist despite optimal medical treatment.
In detail
Pharmacotherapy is the mainstay of treatment. Intranasal corticosteroids effectively control inflammation in the early and late phases of the allergic response. Antihistamines relieve sneezing, itching and runny nose. Combination sprays provide added benefit for moderate-to-severe disease. Saline irrigation helps clear allergens and mucus.
Allergen immunotherapy (SLIT or SCIT) can reduce symptoms, decrease medication needs and modify the long-term course of the disease. In studies, appropriate treatment results in significant symptom relief and improved quality of life.
Surgery does not treat the underlying allergic inflammation; it only addresses anatomical obstruction. Guidelines recommend inferior turbinate reduction only when nasal airway obstruction and enlarged turbinates have failed medical management. Even after surgery, medical therapy and avoidance measures are usually continued.
A common belief
A common belief is that surgery treats the allergy.
What actually happens
It does not. Surgery only opens the nasal passage; the allergic inflammation remains and still needs medical treatment.
Your next step at Jaipur Hospital
Start with a medical plan tailored to your severity and triggers. Give intranasal corticosteroids at least two to four weeks for full effect. If symptoms remain uncontrolled after optimised medical therapy and avoidance, the doctor will reassess for adherence, alternative diagnoses or immunotherapy candidacy. Surgery is a later step, not a first option.
FAQ library
Questions and answers about allergic rhinitis management
When you contact us
Get your allergy plan started
Contact Jaipur Hospital for an ENT consultation, in-house testing and a clear treatment plan with cost estimate and cashless help.
- A consultation with an ENT surgeon in the OPD
- Your scans and reports reviewed, with tests done in-house if you need them (laboratory, X-ray and imaging)
- Your options explained in plain words, including whether you need surgery at all
- A cost estimate before you decide
- Help with cashless treatment under RGHS, MAA Yojana, CGHS and empanelled insurers and TPAs
- Follow-up visits after your treatment
Overview
Allergic Rhinitis Management: what to know
What allergic rhinitis is and how it happens
- 20% to 30% Population affected
- 15% Develop asthma
Allergic rhinitis is a chronic, IgE-mediated type 2 inflammatory disease that affects both adults and children. It is an allergic disorder of the nose and eyes affecting about a fifth of the general population. In India, allergic rhinitis affects 20% to 30% of people, and 15% of those people go on to develop asthma.
The condition is caused by immunoglobulin E (IgE)-mediated reactions to inhaled allergens. Sensitisation to inhaled allergens starts in the first year of life; indoor allergen sensitisation comes before pollen sensitisation. The clinical manifestation of allergic rhinitis is influenced by both the early and late phases of the allergic reaction in the nose.
The early phase occurs within minutes of allergen exposure, when histamine, proteases, and cytokines are released, causing sneezing, runny nose, and itching. The late-phase response, which happens hours later, is characterised by nasal obstruction and hyperreactivity due to eosinophil and Th2 cell-predominant inflammation.
Recurrent symptoms, typically nasal congestion, frequently last because cytokines and mediators produced in the early stages result in a second cellular inflammatory reaction that lasts for 4 to 8 hours. Priming describes increased nasal responsiveness to an allergen with repeated exposure, and it can also be caused by air pollution.
The "one airway, one disease" approach demonstrates how allergic rhinitis is frequently linked to conjunctivitis and/or asthma. Allergic rhinitis has traditionally been classified as seasonal or perennial based on sensitivity to cyclic pollens or year-round allergens such as dust mites, animal dander, cockroaches, and moulds. Following the internationally prescribed ARIA guidelines, allergic nasal illness is now classified as mild or moderate-to-severe, intermittent or persistent.
Symptoms of allergic rhinitis and warning signs needing same-day care
- Sudden severe difficulty breathing
- Swelling of face or throat
- Wheezing not improving with usual inhaler
- Signs of anaphylaxis
Classic symptoms include:
- Sneezing
- Rhinorrhea (runny nose)
- Nasal congestion
- Itching of the nose and eyes
- Postnasal drip
Clear nasal secretions are frequently seen, along with enlarged turbinates and a typically pale and slack nasal mucosa. Allergic rhinitis often co-occurs with asthma and conjunctivitis. It can be associated with sleep disturbance, fatigue, irritability, depression, inability to concentrate at work or school, and work absenteeism, thus exerting an adverse impact on quality of life.
It reduces quality of life and school and work performance. It is a frequent reason for office visits in general practice.
Warning signs that need urgent care the same day include sudden severe difficulty breathing, swelling of the face or throat, wheezing that does not improve with your usual inhaler, or signs of a severe allergic reaction (anaphylaxis) such as widespread hives, dizziness, or collapse. These are not typical allergic rhinitis symptoms and require immediate medical attention.
Causes and who is at higher risk
- IgE-mediated reaction
- Inhaled allergens trigger immune response
- Early sensitisation
- Indoor allergens before pollen in first year
- Genetic factors
- Family history of atopy increases risk
- Environmental stressors
- Air pollution and microbes affect immunity
Allergic rhinitis is caused by immunoglobulin E (IgE)-mediated reactions to inhaled allergens. The main stimulus to the development of noninjection routes was the problem of the safety of injected SIT. Sensitisation to inhaled allergens starts in the first year of life; indoor allergen sensitisation comes before pollen sensitisation.
In the second to fourth decades of life, allergic rhinitis is most common, after which it gradually declines. The signs of rhinitis commonly peak in the second, third, and fourth decades of life after beginning in early childhood.
Although there are genetic determinants of total IgE levels and specific allergen sensitisation, neither the kind of atopic illness nor specific sensitivities seems to be heritable as simple genetic traits.
The chance of developing allergic rhinitis was found to be correlated with polymorphisms of transcription factors GATA binding protein 3, trans-acting T-cell-specific transcription factor, and interleukin (IL)-13 in a cohort of children followed up to age 10. Risk factors include inhalant and occupational allergens, as well as genetic factors.
Due to underlying genetic and immunologic differences, some populations are more susceptible. Genes TSLP, GATA3, IL-4, IL-13, and IL-33, which control Th2 cell differentiation and IgE synthesis, have polymorphisms found by genome-wide association studies. Variants in IL1RL1 and HLA-DQ have also been linked to increased incidence of atopy and allergic airway inflammation.
Those who have a family history of atopic diseases including asthma, eczema, or allergic conjunctivitis exhibit a genetically primed immune response marked by increased Th2 polarisation and eosinophilia. Air pollution and microbiological exposure are environmental stressors that can cause epigenetic changes, such as changed DNA methylation, that affect immunological tolerance and disease manifestation.
Several comorbid disorders have been associated with allergic rhinitis and include asthma, sinusitis, otitis media, nasal polyposis, lower respiratory tract infection, and dental malocclusion.
How allergic rhinitis is diagnosed: examination and tests
- Clinical history and examination Symptoms and nasal findings
- Assess for associated conditions Asthma, conjunctivitis, etc.
The diagnosis of allergic rhinitis is based on the clinical history and, if needed, on skin tests or the presence of serum-specific IgE antibodies to allergens.
Clinicians should make the clinical diagnosis when patients present with a history and physical examination consistent with an allergic cause and one or more of the following symptoms: nasal congestion, runny nose, itchy nose, or sneezing. Findings consistent with an allergic cause include clear rhinorrhea, nasal congestion, pale discoloration of the nasal mucosa, and red and watery eyes.
The pale discoloration of the nasal mucosa is a clinical observation made by experts to aid in diagnosis. A definite diagnosis is made based on three symptoms (sneezing and nasal itch, rhinorrhea, and nasal congestion), patient history of allergen exposure, and critical clinical examination findings (clear rhinorrhea, pale discoloration of nasal mucosa, and watery and red eyes).
Medical history, physical examination, and, if necessary, nasal endoscopy are used to diagnose allergic rhinitis. In certain cases, testing for allergen-specific IgE (skin prick or serum-specific IgE) is also performed. Skin testing for seasonal and perennial aeroallergens is useful to distinguish non-allergic rhinitis from allergic rhinitis and to show if IgE antibodies are present or absent.
For almost a century, clinical skin prick testing (SPT) has been used to help diagnose atopic, IgE-mediated disorders. SPT has been proven to be a reliable and effective way to identify allergies. SPT enables the assessment of several allergens in a single session, with results available in 15 to 20 minutes.
The nasal allergen provocation test is a sensitive, specific, and reproducible method, but it takes a long time and requires expert personnel.
Clinicians should perform and interpret, or refer to a clinician who can perform and interpret, specific IgE (skin or blood) allergy testing for patients with a clinical diagnosis who do not respond to empiric treatment, or when the diagnosis is uncertain, or when knowledge of the specific causative allergen is needed to target therapy.
Clinicians should assess patients for, and document in the medical record, the presence of associated conditions such as asthma, atopic dermatitis, sleep-disordered breathing, conjunctivitis, rhinosinusitis, and otitis media. Routine sinonasal imaging must not be performed in patients presenting with symptoms consistent with allergic rhinitis. It may be considered in patients who do not respond to therapy.
Referral to an allergist/immunologist should be considered for patients with severe or refractory disease, uncertainty regarding clinically relevant allergens, consideration of allergen immunotherapy, or substantial impairment in quality of life. Referral to an otolaryngologist may be appropriate when structural abnormalities, chronic rhinosinusitis, nasal polyps, recurrent epistaxis, or other conditions requiring endoscopic evaluation or surgical management are suspected.
Non-surgical treatment options for allergic rhinitis and when surgery is advised
Management of allergic rhinitis is based on symptom severity, symptom frequency, allergen exposure, patient preferences, and the presence of comorbid conditions such as asthma. Treatment typically includes allergen avoidance when feasible, pharmacotherapy, and allergen immunotherapy for selected patients. Pharmacologic therapy is the mainstay of treatment for most patients, with intranasal corticosteroids serving as first-line therapy for persistent or moderate-to-severe disease.
Patients with intermittent symptoms are often adequately managed with second-generation oral or intranasal antihistamines. Intranasal corticosteroids are the most effective monotherapy for persistent or moderate-to-severe allergic rhinitis and are recommended as first-line treatment for most patients.
Second-generation antihistamines are used to treat mild allergic rhinitis and are generally preferred over first-generation agents because they provide similar efficacy with fewer sedating and anticholinergic adverse effects. First-generation antihistamines should generally be avoided, particularly in young children and older adults, because of their unfavorable adverse-effect profile.
For moderate-to-severe allergic rhinitis or symptoms inadequately controlled with monotherapy, combination treatment with an intranasal corticosteroid and intranasal antihistamine may provide greater symptom control than either agent alone. Fixed-dose combination intranasal sprays, such as azelastine/fluticasone and olopatadine/mometasone, are available.
Treatment response should be reassessed periodically, with escalation, de-escalation, or changes in therapy guided by symptom control, adherence, medication technique, adverse effects, and patient preferences. Patients with persistent symptoms despite optimised pharmacotherapy should be evaluated for adherence, alternative diagnoses, and candidacy for allergen immunotherapy.
Allergen immunotherapy (AIT) represents the only currently available treatment that targets the underlying pathophysiology, and it may have a disease-modifying effect. Either the subcutaneous (SCIT) or sublingual (SLIT) routes may be used. SCIT and SLIT are recommended for both seasonal and perennial allergic rhinitis for short-term benefit.
To achieve long-term efficacy, it is recommended that a minimum of 3 years of therapy is used. Clinicians should offer, or refer to a clinician who can offer, immunotherapy (sublingual or subcutaneous) for patients who have inadequate response to symptoms with pharmacologic therapy with or without environmental controls.
Sublingual immunotherapy (SLIT) is an effective alternative for selected patients and is available for specific allergens, including certain grass pollens, ragweed pollen, and house dust mites. SLIT is generally most appropriate for patients with clinically relevant sensitisation to allergens covered by currently available products. It may be less suitable for patients with polysensitisation requiring treatment for multiple unrelated allergens.
Subcutaneous immunotherapy (SCIT) has been shown to reduce allergic rhinitis symptoms and medication requirements and may provide sustained clinical benefit after treatment is completed. Therapy is typically administered over 3 to 5 years and should be performed by appropriately trained clinicians because systemic allergic reactions, including anaphylaxis, may occur.
Environmental control measures should target clinically relevant allergens identified through the patient's history and, when indicated, allergy testing. Broad or indiscriminate allergen avoidance is generally not recommended. For seasonal allergens, limiting outdoor exposure during periods of high pollen counts, keeping windows closed, using air conditioning when appropriate, and showering after outdoor activities may help reduce allergen exposure.
For indoor allergens, strategies should be individualised according to the identified trigger. Dust mite exposure may be reduced by using a comprehensive, multicomponent approach, such as allergen-impermeable mattress and pillow covers, washing bedding regularly in hot water, and maintaining low indoor humidity, as single isolated interventions are unlikely to yield substantial clinical benefit.
Mold exposure may be reduced by controlling indoor moisture, and pet avoidance remains the most effective strategy for animal allergy, although limiting pet access to bedrooms and using high-efficiency particulate air (HEPA) filtration may provide some benefit when removal is not feasible. Patients with occupational allergy should minimise exposure whenever possible or use appropriate workplace protective measures.
Avoidance of nonspecific irritants, including tobacco smoke, air pollution, strong odours, and rapid temperature changes, may also improve symptoms in susceptible individuals. Smoking cessation and avoidance of secondhand smoke and other airborne irritants are recommended because these exposures may worsen rhinitis symptoms.
Adherence to prescribed pharmacotherapy before and during anticipated allergen exposure, particularly during seasonal pollen periods, may help prevent symptom exacerbations. Surgery is not a treatment for the underlying allergic disease but may be indicated for associated structural abnormalities or comorbid conditions, including chronic rhinosinusitis, severe septal deviation, inferior turbinate hypertrophy, nasal polyps, or other anatomic causes of persistent nasal obstruction.
Clinicians may offer, or refer to a surgeon who can offer, inferior turbinate reduction in patients with allergic rhinitis with nasal airway obstruction and enlarged inferior turbinates who have failed medical management.
Preparing for Allergic Rhinitis Management
Do
- Note symptom patterns and triggers
- Bring current medicine list
- Carry previous allergy test reports
- Pause antihistamines if told
Allergic rhinitis management at Jaipur Hospital is an outpatient process. You do not need to fast or stay in hospital. Before your first visit, note down when your symptoms are worst, what seems to trigger them, and any medicines you have already tried.
Bring a list of current medicines, including any eye drops or skin creams, so your doctor can check for interactions. If you have had previous allergy tests or blood reports, carry those as well. Your surgeon may ask you to stop antihistamines for a few days before skin prick testing, because they can hide the reaction.
You will be told exactly which medicines to pause and for how long. No special diet or bowel preparation is needed. Wear comfortable clothing and bring an attendant if you wish, though most patients manage the visit on their own.
How Allergic Rhinitis Management Is Done
Treatment is tailored to your symptom pattern, severity, and the allergens identified on testing. The main options are:
- Intranasal corticosteroids: a daily spray that reduces inflammation in the nasal lining. This is first-line treatment for persistent or moderate-to-severe symptoms.
- Antihistamines: oral tablets or nasal sprays that block histamine. Second-generation oral antihistamines are preferred because they cause less drowsiness. Intranasal antihistamines work faster and have fewer systemic effects.
- Sublingual immunotherapy (SLIT): drops or tablets placed under the tongue daily. SLIT is used for specific allergens such as grass pollen, ragweed, and house dust mite. It is generally most appropriate when you are sensitised to allergens covered by available products.
- Subcutaneous immunotherapy (SCIT): allergy shots given under the skin. The build-up phase involves weekly or twice-weekly injections for up to six months, followed by a maintenance phase of monthly injections for three to five years.
Your surgeon will advise which option suits you. On the day of a SCIT visit, you receive the injection in the clinic and wait about 30 minutes for observation. SLIT doses are taken at home after the first dose is given under medical supervision. Intranasal sprays and oral medicines are started at home with instructions on correct technique. Saline nasal irrigation may be added to wash out allergens and mucus.
Risks and Possible Complications of Allergic Rhinitis Management
- Intranasal corticosteroids
- Nasal irritation, dryness, mild bleeding
- Oral antihistamines
- Mild drowsiness, dry mouth, headache
- SCIT local reactions
- Redness, warmth, itching, swelling at injection site
- SLIT local reactions
- Mouth itching or throat irritation
Intranasal corticosteroids are well tolerated. Newer second-generation sprays have very low systemic absorption, so systemic side effects are uncommon. Nasal irritation, dryness, or mild bleeding can occur; using the correct spray technique reduces this. Oral antihistamines may cause mild drowsiness, dry mouth, or headache. First-generation antihistamines are avoided because of stronger sedation and anticholinergic effects.
Intranasal decongestant sprays must not be used for more than three to five days, as they can cause rebound congestion (rhinitis medicamentosa) and damage the nasal lining.
For SCIT, redness, warmth, itching, or swelling at the injection site are common. Systemic reactions such as hives, itching elsewhere, or trouble breathing are less common. Anaphylaxis is rare but possible, which is why shots are given in a setting with emergency care available. You must report any delayed reaction within 24 hours.
In one study, bronchospasm occurred in three patients and was linked to incorrect technique. Beta-blockers and ACE inhibitors can increase the risk of severe reactions or make them harder to treat. SLIT commonly causes local mouth itching or throat irritation; severe systemic reactions are very rare. Montelukast carries a boxed warning for neuropsychiatric effects and is reserved for selected patients. Short courses of oral steroids are used only for severe flare-ups.
Recovery and Aftercare for Allergic Rhinitis Management
- Symptom control starts Two to four weeks with medicines
- After SCIT injection Stay 30 minutes in clinic for observation
- Local reactions settle Within a few hours after SCIT
- Follow-up visits Check response, adjust doses, review technique
There is no surgical recovery. Symptom control with intranasal corticosteroids and antihistamines usually begins within two to four weeks. You will be shown how to aim the spray away from the nasal septum to reduce bleeding. Saline rinses can be used before the steroid spray to clear mucus.
For SCIT, you stay in the clinic for about 30 minutes after each shot. Local reactions at the injection site settle within a few hours. If you notice increasing swelling, hives, breathing difficulty, or dizziness after leaving, return to the emergency department or call the hospital.
For SLIT, the first dose is taken under supervision; after that you continue daily at home. Keep a symptom diary and note any side effects. Follow-up visits are scheduled to check response, adjust doses, and review inhaler or spray technique. If symptoms persist despite optimised pharmacotherapy, your doctor will reassess the diagnosis, check adherence, and discuss immunotherapy candidacy. Smoking cessation and avoiding second-hand smoke improve outcomes. Environmental controls targeted to your specific allergens help reduce exposure.
Results of Allergic Rhinitis Management
In studies, intranasal corticosteroids are the most effective monotherapy for persistent or moderate-to-severe allergic rhinitis and improve nasal and eye symptoms as well as sleep quality. Combination therapy with an intranasal corticosteroid and intranasal antihistamine gives greater symptom control than either alone for moderate-to-severe disease. Fixed-dose combination sprays are available.
Allergen immunotherapy is the only disease-modifying treatment. In appropriately selected patients with confirmed IgE-mediated disease, immunotherapy reduces symptoms, decreases medication use, and can modify the long-term course of allergic disease. SCIT has shown sustained clinical benefit after treatment ends. SLIT is effective for specific allergens such as grass pollen, ragweed, and house dust mite.
The strongest evidence for long-term benefit is documented for grass allergen immunotherapy, especially tablets, where benefit persists after stopping. A minimum of three years of therapy is recommended for long-term efficacy. In one follow-up study, clinical efficacy was not maintained after discontinuation of local nasal immunotherapy, suggesting a pre-seasonal course may be needed each year.
However, a prospective observational study documented three to five years of lasting efficacy in some patients after stopping. Experts do not know exactly how long allergy shots work after you stop; some people remain symptom-free while others see allergies return within a few years. Immunotherapy may also prevent children with allergic rhinitis from developing asthma. Appropriate treatment improves quality of life, school and work productivity.
Cost and Insurance for Allergic Rhinitis Management in Jaipur
The typical yearly cost for medical management ranges from ₹2,000 to ₹15,000. A full course of immunotherapy (three to five years) typically costs ₹50,000 to ₹1,00,000. The final amount depends on the type of immunotherapy (SLIT or SCIT), the number of allergens treated, the brand of extracts or sprays used, and how long you need treatment.
Medical costs for allergic rhinitis are large, and avoidable costs from lost work productivity are even larger. LNIT avoids injection costs and loss of time because it is self-administered at home.
Jaipur Hospital accepts RGHS, MAA Yojana, CGHS, and a panel of private insurers and TPAs. Coverage for immunotherapy varies by scheme and policy; some plans cover the extracts and administration, others only cover consultations and medicines. Ask your insurer what is included under allergy treatment. The hospital's insurance desk can help verify benefits and process claims.
No advance deposit is required for OPD visits. You pay for medicines at the in-house pharmacy and for each immunotherapy visit as per the schedule.
