

Obstetrics and Gynaecology · Jaipur Hospital
Fibroids and Uterine Conditions in Jaipur
Heavy periods and pelvic pain? Get clear assessment and a treatment plan at Jaipur Hospital.
- Serving Jaipur since 1991 (35 years)
- NABH accredited
- 24×7 emergency & ICU
- Cashless: RGHS, MAA Yojana, CGHS + 22 insurers
- Operation time
- 1 to 3 hours
- Anaesthesia
- General or spinal anaesthesia
- Recovery
- 2 to 6 weeks
- Price
- ₹50,000 to ₹2,00,000typical range in India; ask us for an estimate
When periods disrupt daily life
Heavy bleeding and pelvic pressure that won't go away
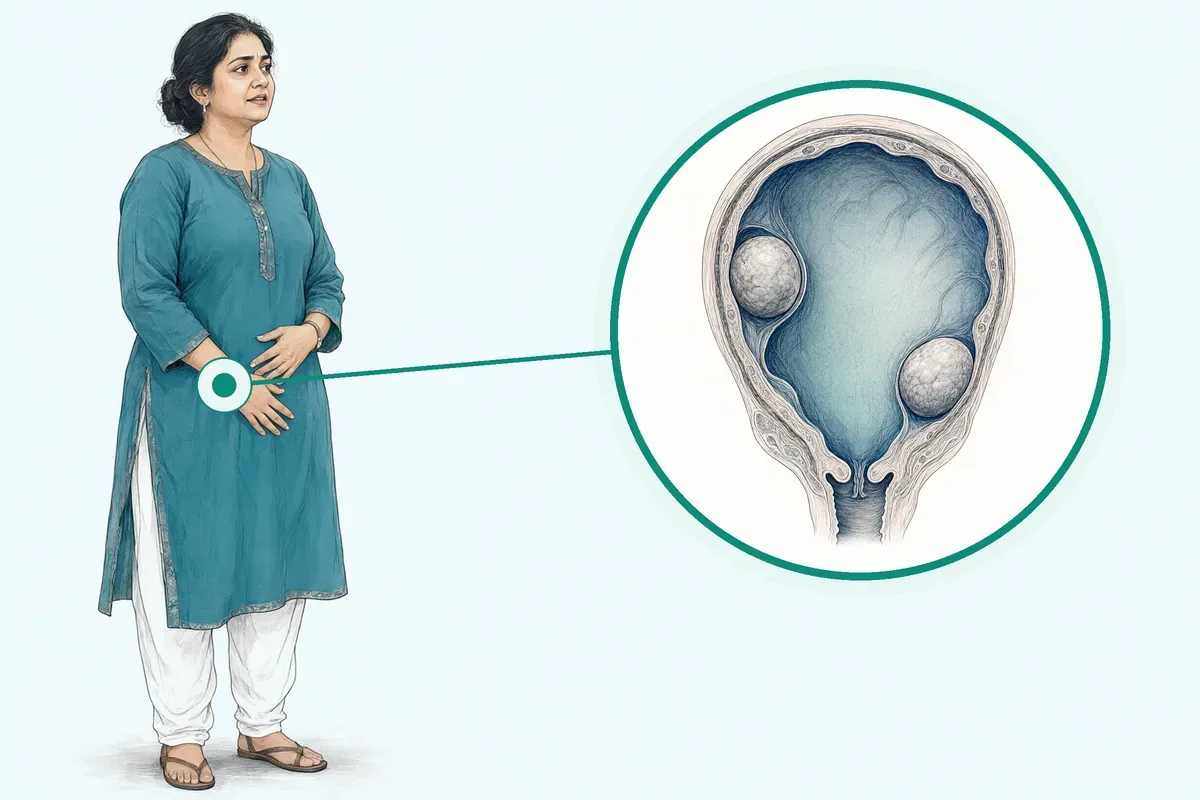
Fibroids are common benign growths in the uterus. Many women have no symptoms, but others face heavy periods, anaemia, pelvic pain, frequent urination or difficulty getting pregnant.
-
Periods that last too long
Bleeding longer than seven days or soaking through pads every hour can lead to anaemia and fatigue.
-
Pelvic pain and pressure
Large fibroids press on the bladder and bowel, causing frequent urination, constipation or a constant heavy feeling.
-
Fertility worries
Fibroids can block fallopian tubes or change the uterine shape, making it harder to conceive or carry a pregnancy.
-
Work and home disrupted
Unpredictable bleeding and pain force many women to miss work, skip social events or limit daily activities.
Fibroids are the most common pelvic tumours in women of reproductive age, driven by genetic changes and hormone-sensitive extracellular matrix growth.
Why Jaipur Hospital
You worry that heavy bleeding will exhaust you, that pain will keep you from work or caring for your family, and that surgery might cost more than you can afford.
Your care plan
Your first steps with us
- 1 Call or visit OPD for gynaecology consultation
- 2 Complete scans and blood tests in-house
- 3 Discuss medical or surgical options with your surgeon
- 4 Schedule procedure and plan recovery with attendant support
How the operation is done
Surgery is performed under general or spinal anaesthesia and usually takes one to three hours. Hospital stay is typically one to three nights. Your surgeon chooses the approach based on fibroid size, number, location and your fertility goals.
-
Laparoscopic myomectomy
Keyhole surgery to remove fibroids while keeping the uterus, often chosen when future pregnancy is desired.
-
Hysteroscopic myomectomy
No-incision removal of submucosal fibroids through the vagina, usually with faster recovery.
-
Laparoscopic hysterectomy
Keyhole removal of the uterus for women who have completed their family or have severe symptoms.
-
Uterine artery embolisation
Interventional radiology procedure that blocks blood supply to shrink fibroids without surgery.
Why patients trust us
- 1991 Serving Jaipur for 35 years
- NABH Accredited hospital
- 3 Obstetrics and Gynaecology consultants
- 24×7 Emergency, ICU and ambulance
- 25 Cashless schemes and insurers
What research shows about treatment outcomes
-
2 to 4 weeks recovery
After laparoscopic myomectomy, most patients recover at home in two to four weeks.
-
Days to recover
Hysteroscopic myomectomy recovery can be just a matter of days.
-
New fibroids may grow
Younger women with many fibroids have a higher chance of new fibroids developing after myomectomy.
If it is left untreated
Untreated symptomatic fibroids can worsen anaemia from heavy bleeding, increase pelvic pain and pressure on the bladder or bowel, and may contribute to infertility or pregnancy complications such as preterm labour.
Life after treatment
Most women find periods become lighter and more regular, pelvic pressure eases, and daily routines return to normal within weeks.
-
Lighter, regular periods
Most people experience a lighter and more regular period after myomectomy.
-
Less pelvic pressure
Removing fibroids usually relieves the heavy feeling and urinary frequency caused by an enlarged uterus.
-
Return to work and home
Recovery typically takes two to six weeks depending on the procedure, after which normal activities resume.
-
Fertility preserved when possible
Myomectomy keeps the uterus intact, so pregnancy remains an option for many women.



Frequently asked questions
Questions patients ask about fibroids and uterine conditions
Which problems are assessed under fibroids and uterine conditions?
In short
Jaipur Hospital assesses uterine fibroids, adenomyosis, and related conditions such as abnormal uterine bleeding, pelvic pain, pressure symptoms, and infertility linked to these conditions. Our gynaecology team evaluates the size, number, and location of fibroids and their impact on your daily life and reproductive plans.
In detail
Uterine fibroids are benign monoclonal neoplasms of the myometrium and the most common pelvic tumours in women of reproductive age. They are heterogeneous in composition, size, and location. Adenomyosis involves endometrial tissue growing into the uterine muscle.
Both can cause heavy bleeding, anaemia, pelvic pain, urinary frequency, constipation, back pain, and infertility. Some women have no symptoms at all. Assessment includes understanding how these affect your quality of life and future fertility wishes.
A common belief
Many women think fibroids always need surgery.
What actually happens
In fact, most fibroids are asymptomatic and only need monitoring. The decision depends on how much they affect your daily life and your fertility plans.
Your next step at Jaipur Hospital
At your first visit, the doctor will take a detailed history, perform a pelvic examination, and usually order an ultrasound scan. Further imaging such as MRI may be needed for complex cases. You will receive a clear explanation of findings and a personalised care plan.
How will the doctor decide which tests I need?
In short
The gynaecologist at Jaipur Hospital selects tests based on your symptoms, examination findings, and reproductive plans. A transvaginal or abdominal ultrasound is usually the first imaging test to map fibroid number, size, and location. MRI may be added for complex cases or surgical planning. Blood tests include haemoglobin, iron studies, and sometimes hormone levels.
In detail
Evidence indicates fibroids vary widely in size, location, and clinical behaviour. Ultrasound is cost-effective and widely available for initial mapping. MRI provides superior soft-tissue contrast, defines the junctional zone for adenomyosis, and helps plan myomectomy by showing the relationship to the uterine cavity and serosa.
Blood tests quantify anaemia severity and guide preoperative optimisation. Hormonal assays may be used if medical therapy is considered. The doctor avoids unnecessary tests by targeting each modality to a specific clinical question.
A common belief
Some patients expect every scan at once.
What actually happens
The doctor orders each test to answer a specific question: ultrasound for mapping, MRI for surgical detail, bloods for safety. This avoids delay and extra cost.
Your next step at Jaipur Hospital
Most tests are available in-house at the diagnostic laboratory and radiology department. Ultrasound results are often available the same day. MRI may be scheduled within a few days. Blood reports typically return within hours. The surgeon will review all results with you at a follow-up visit or by phone.
How soon should I expect improvement after the chosen treatment for uterine fibroids?
In short
At Jaipur Hospital, the timing of improvement depends on the treatment you receive. After surgical removal of fibroids, most people experience lighter and more regular periods once healing is complete. Medical treatments such as ulipristal acetate can control bleeding within days, with median times to amenorrhea of five to seven days in studies. Minimally invasive procedures usually allow faster return to normal activities than open surgery.
In detail
Recovery time varies by technique. After a hysteroscopic myomectomy, full recovery can be just a matter of days. After a laparoscopic myomectomy, recovery at home is about two to four weeks.
With an open myomectomy, full recovery before getting back to normal activities can take up to six weeks. Studies show that uterine bleeding was controlled in 90% to 98% of patients receiving ulipristal acetate, with amenorrhea occurring in 79% after the first course.
Median fibroid volume reduction was 45% after the first course of medical treatment and up to 72% after repeated courses. For uterine artery embolisation, symptom improvement typically occurs over several weeks as fibroids shrink. Your surgeon will give you a personalised timeline based on the procedure performed.
A common belief
People often expect instant relief after any procedure.
What actually happens
In reality, your body needs time to heal, especially after abdominal surgery. Medical treatments also need a few days to show effect on bleeding.
Your next step at Jaipur Hospital
You will receive post-operative instructions before discharge, including activity restrictions, wound care and follow-up dates. Most patients need help at home for the first one to three days. Return to work depends on the nature of your job and the type of procedure.
A follow-up visit is usually scheduled within two weeks. To get a clear recovery plan for your situation, book a consultation at Jaipur Hospital.
Does this uterine condition need treatment if I have few symptoms?
In short
At Jaipur Hospital, uterine fibroids that cause few or no symptoms often do not need immediate treatment. Most women with fibroids are asymptomatic. Treatment is usually considered when fibroids cause significant symptoms such as heavy bleeding, anaemia, pelvic pain, pressure, urinary frequency, constipation or infertility. If your fibroids are small and not causing problems, watchful waiting with periodic ultrasound monitoring is a common approach.
In detail
Evidence shows that uterine fibroids are extremely common and some do not require any treatment. They are the most common pelvic tumours among women of reproductive age, yet many remain undetected.
The decision to treat depends on symptom severity, fibroid size and location, your age and fertility plans. Asymptomatic fibroids may be monitored with regular clinical exams and imaging.
Medical treatments such as GnRH agonists, selective progesterone receptor modulators or other agents are typically reserved for symptomatic cases. Surgical options including myomectomy, hysterectomy or uterine artery embolisation are considered when symptoms affect quality of life or fertility. Your gynaecologist will assess whether the fibroids are growing or changing over time.
A common belief
A common fear is that every fibroid must be removed.
What actually happens
In reality, asymptomatic fibroids are often safely monitored. Unnecessary surgery carries its own risks.
Your next step at Jaipur Hospital
If you have been diagnosed with fibroids but have minimal symptoms, schedule a routine review to discuss monitoring intervals. Bring any previous imaging reports. Your doctor will advise how often to repeat ultrasound and what symptoms should prompt earlier review.
No treatment is needed unless symptoms develop or change. To set up a monitoring plan, book a consultation at Jaipur Hospital.
How can I decide whether to seek advice about myomectomy for fibroids?
In short
Consider myomectomy advice if fibroids cause heavy bleeding, pelvic pain, pressure symptoms, or infertility and you want to keep your uterus. Jaipur Hospital evaluates fibroid size, number, and location to guide the decision. Myomectomy is a recognised option for fertility preservation. Your surgeon will discuss whether medical or surgical management fits your situation.
In detail
Evidence indicates myomectomy is an alternative to hysterectomy for women who wish to become pregnant. The procedure removes fibroids while preserving the uterus. Three main approaches exist: open, laparoscopic, and hysteroscopic. The choice depends on fibroid characteristics.
Nonsurgical options like medication or uterine artery embolisation may be tried first. Surgery is usually considered when symptoms affect quality of life or fertility. Complications can include infection, bleeding, injury to nearby organs, and scarring.
New fibroids may develop later, particularly in younger women with many fibroids. Your gynaecologist will weigh symptom severity, reproductive plans, and fibroid mapping before recommending myomectomy.
A common belief
Some women wait until symptoms are severe.
What actually happens
Earlier evaluation gives more options, including medical management or less invasive surgery.
Your next step at Jaipur Hospital
Track your symptoms: bleeding pattern, pain levels, and any pressure on bladder or bowel. Schedule an OPD visit with recent imaging. The surgeon will explain each technique and typical recovery times. Hospital stay is usually one to three nights.
How could fibroids or their treatment affect future pregnancy?
In short
Fibroids themselves can affect fertility and pregnancy outcomes. Treatment effects vary by procedure. Jaipur Hospital assesses each case individually. Myomectomy preserves the uterus for pregnancy but carries a risk of uterine scarring. Hysterectomy ends fertility. Embolisation may affect ovarian reserve. Your surgeon will explain risks based on fibroid location and chosen treatment.
In detail
Evidence links fibroids to poor obstetrical outcomes, including infertility and pregnancy complications. Submucosal fibroids distorting the cavity are most likely to impair implantation. Intramural fibroids may also reduce fertility.
Myomectomy can improve pregnancy chances but new fibroids may grow later, especially in women under 40 with multiple fibroids. Scarring from surgery can affect uterine integrity. Caesarean delivery may be recommended after myomectomy depending on the uterine incision. Hysterectomy makes pregnancy impossible.
Uterine artery embolisation has uncertain effects on ovarian function and future pregnancy. Medical treatments like GnRH agonists are temporary and not used during pregnancy. The impact depends on fibroid type, treatment choice, and individual healing.
A common belief
Many assume fibroid treatment always protects fertility.
What actually happens
The truth varies: submucosal fibroids hurt implantation most, and surgery type matters for uterine strength.
Your next step at Jaipur Hospital
Share your pregnancy timeline with the gynaecologist. Bring all imaging reports. Ask about the recommended waiting period after any procedure before trying to conceive. Follow-up scans may be needed.
Which symptoms should prompt me to see a specialist?
In short
You should see a specialist at Jaipur Hospital if you experience heavy or prolonged menstrual bleeding, bleeding between periods, pelvic pain or pressure, frequent urination, difficulty emptying the bladder, constipation, backache, pain during intercourse, or difficulty conceiving. These symptoms suggest fibroids or adenomyosis affecting your quality of life.
In detail
Evidence indicates most women with fibroids are asymptomatic, but approximately 30 percent present with severe symptoms. Abnormal uterine bleeding can lead to anaemia. Pelvic pain and pressure result from the ECM-rich rigid structure of fibroids and uterine enlargement.
Urinary frequency and constipation occur when enlarged uterus compresses the bladder or rectum. Infertility and pregnancy complications are linked to cavity distortion and altered uterine contractility. Early evaluation prevents worsening anaemia and preserves fertility options.
- Evidence indicates most women with fibroids are asymptomatic, but approximately 30 percent present with severe symptoms.
A common belief
Women often dismiss heavy periods as normal or attribute urinary frequency to ageing.
What actually happens
However, these can signal significant uterine enlargement or cavity distortion that worsens over time.
Your next step at Jaipur Hospital
Track your symptoms for one to two cycles, noting bleeding pattern, pain severity, and impact on daily activities. Bring any previous imaging or blood reports to the appointment. The gynaecologist will perform a pelvic examination and may order an ultrasound or MRI.
How will the results change my care plan?
In short
Test results at Jaipur Hospital directly shape your care plan by defining fibroid type, size, location, and the severity of anaemia. Submucosal fibroids distorting the cavity often lead to hysteroscopic removal. Large intramural or subserosal fibroids may need laparoscopic myomectomy or hysterectomy. Adenomyosis on MRI may steer treatment toward medical therapy or hysterectomy. Severe anaemia may require iron infusion or transfusion before surgery.
In detail
Evidence shows treatment is tailored to fibroid mapping and patient goals. Hysteroscopic myomectomy suits submucosal fibroids with no incision. Laparoscopic myomectomy preserves the uterus for fertility. Laparoscopic hysterectomy is chosen when family is complete or symptoms are severe. Uterine artery embolisation shrinks fibroids without surgery.
Medical options like GnRH agonists or progesterone receptor modulators can control bleeding and shrink fibroids temporarily. The surgeon integrates imaging, blood work, and your preferences to recommend the most appropriate pathway.
A common belief
Patients sometimes think one treatment fits all.
What actually happens
In reality, a 2 cm submucosal fibroid and a 10 cm intramural fibroid need completely different approaches. The plan is built around your specific anatomy and goals.
Your next step at Jaipur Hospital
After results are ready, the surgeon will explain the findings, discuss each suitable option with risks and recovery timelines, and answer your questions. You will decide together on the next step, whether it is a procedure date, medical trial, or further review.
What should I do if symptoms persist or worsen after treatment for uterine fibroids?
In short
At Jaipur Hospital, if your symptoms persist or worsen after treatment for uterine fibroids, you should contact your surgeon or the hospital without delay. Warning signs include fever, severe abdominal pain, heavy vaginal bleeding, or any new symptom that concerns you. Prompt assessment helps identify complications such as infection, bleeding or injury to nearby organs, which can occur after any surgery.
In detail
Evidence indicates that possible complications of myomectomy include infection, bleeding, injury to nearby organs and scarring. If you have a myomectomy, contact your provider if you experience fever, severe abdominal pain or heavy vaginal bleeding.
All surgeries have the potential for complications, which is why your provider may suggest nonsurgical treatment options first.
For medical treatments, side effects such as hot flashes can occur; moderate-to-severe hot flashes were reported in 11% to 40% of patients in studies depending on the drug. New fibroids may grow after a myomectomy, especially in younger people under age 40 with many fibroids.
Persistent symptoms could also mean the original treatment did not address all fibroids or that a different approach is needed. Your surgeon will evaluate whether further imaging, medication adjustment or a repeat procedure is appropriate.
A common belief
Some patients wait for their next routine check-up even when they have alarming symptoms.
What actually happens
Early contact allows quicker management of complications or recurrence. New fibroids can also develop, especially in younger women.
Your next step at Jaipur Hospital
Keep your discharge summary and medication list handy. If you notice warning signs, call the hospital numbers or visit the 24×7 emergency department at Jaipur Hospital. Do not wait for your next scheduled appointment if symptoms are severe. Early review allows timely intervention. To arrange a follow-up or discuss ongoing symptoms, book a consultation at Jaipur Hospital.
Can the uterus be preserved when treating uterine fibroids?
In short
At Jaipur Hospital, yes, the uterus can often be preserved when treating uterine fibroids. Myomectomy is a procedure that removes fibroids while keeping the uterus intact. It is a good option if you wish to become pregnant in the future and want to preserve your fertility. There are three main types of myomectomy: open, laparoscopic and hysteroscopic. The choice depends on the size, number and location of the fibroids.
In detail
Evidence confirms that myomectomy is an alternative to hysterectomy, which removes the uterus, cervix and fibroids. Laparoscopic myomectomy preserves the uterus for fertility. Hysteroscopic myomectomy removes submucosal fibroids without any incision.
Uterine artery embolisation is an interventional radiology option that shrinks fibroids while preserving the uterus. However, new fibroids may grow after a myomectomy. Younger people under age 40 with many fibroids are at greater risk of getting more fibroids in the future.
The decision to preserve the uterus also depends on whether you have completed your family, the severity of symptoms, and the feasibility of removing all fibroids safely. Your surgeon will discuss whether uterus-preserving options are suitable for your specific situation.
A common belief
Some patients believe hysterectomy is the only definitive surgery.
What actually happens
In fact, several uterus-preserving techniques exist, though they carry a chance of fibroid recurrence, especially in younger women with multiple fibroids.
Your next step at Jaipur Hospital
If preserving your uterus is important to you, tell your surgeon at the first visit. Fertility goals, fibroid mapping by MRI or ultrasound, and your overall health will guide the recommendation.
You will receive information on the risks, recovery time and likelihood of symptom relief for each uterus-preserving option. To explore whether you are a candidate for uterus-preserving treatment, book a consultation at Jaipur Hospital.
FAQ library
Questions and answers about fibroids and uterine conditions
When you contact us
Get your assessment and plan
Contact Jaipur Hospital for a gynaecology consultation, in-house tests, clear options, a cost estimate and help with cashless schemes.
- A consultation with a gynaecologist in the OPD
- Your scans and reports reviewed, with tests done in-house if you need them (laboratory, X-ray and imaging)
- Your options explained in plain words, including whether you need surgery at all
- A cost estimate before you decide
- Help with cashless treatment under RGHS, MAA Yojana, CGHS and empanelled insurers and TPAs
- Follow-up visits after your treatment
Overview
Fibroids and Uterine Conditions: what to know
What fibroids and adenomyosis are and how they develop
- Uterine fibroids
- Benign growths from the muscle layer of the uterus
- Adenomyosis
- Inner lining grows into the muscle wall
- Hormone driven
- Oestrogen and progesterone stimulate growth
- After menopause
- Fibroids often shrink when hormone levels fall
Uterine fibroids are benign growths that arise from the muscle layer of the uterus. They are the most common pelvic tumours in women of reproductive age. Fibroids contain smooth muscle, fibroblast cells and a large amount of fibrous extracellular matrix that gives them a firm structure.
They vary widely in size, number and position; some women have a single small nodule while others have many large ones.
Adenomyosis is a different condition where the inner lining of the uterus grows into the muscle wall. This makes the uterus thicker and often tender. Both conditions are driven by the hormones oestrogen and progesterone, which stimulate growth of the muscle and the surrounding matrix.
Genetic changes in the MED12 gene are found in the majority of fibroids and appear to be an early step in their formation. Other, less common genetic alterations involve HMGA2, the COL4A5-COL4A6 region and the FH gene. The extracellular matrix acts as a reservoir for growth factors such as TGF‑β and activin‑A, which keep the fibrotic process active. Because fibroids are hormone‑dependent, they often shrink after menopause when hormone levels fall.
Symptoms of fibroids and adenomyosis and when to seek urgent care
- Very heavy bleeding Soaks a pad in an hour or less
- Sudden severe pain Does not settle with simple pain relief
- Fever with pelvic pain May indicate infection
- Dizziness or fainting Suggests significant blood loss
Many women with fibroids have no symptoms at all.
When symptoms occur, they can include:
- Heavy or prolonged menstrual bleeding
- Irregular vaginal bleeding
- Pelvic pain or a feeling of pressure
- Lower back pain
- Frequent urination
- Constipation
- Difficulty becoming pregnant
Adenomyosis typically causes heavy, painful periods and a bulky, tender uterus.
Contact your doctor or attend the emergency department on the same day if you experience:
- Very heavy bleeding that soaks a pad in an hour or less
- Sudden, severe abdominal or pelvic pain that does not settle with simple pain relief
- Fever with pelvic pain
- Dizziness, fainting or shortness of breath suggesting significant blood loss
These signs may indicate severe anaemia, a twisted fibroid, infection or another complication that needs immediate assessment.
Causes and factors that raise the risk of fibroids
- Age and hormones
- Premenopausal women are at higher risk
- Family history
- Having relatives with fibroids raises risk
- Body weight
- Higher BMI, waist‑to‑hip ratio and body fat above 30% increase risk
- Hypertension
- Raised diastolic blood pressure linked to several‑fold higher risk
- Diet
- Green vegetables, fruit and fish lower risk; food additives and soybean milk raise risk
- Ethnicity
- Black women have two‑ to three‑fold higher incidence
The exact cause of each fibroid is not fully known, but several factors increase the likelihood of developing them. Age and being premenopausal are strong risk factors because fibroids grow under the influence of ovarian hormones. A family history of fibroids raises risk.
Higher body weight, increased body mass index, greater waist‑to‑hip ratio and body fat above 30% are all associated with higher risk. Visceral fat in the abdomen adds further risk. Hypertension and raised diastolic blood pressure are linked to a several‑fold increase in risk. Women who have never given birth (nulliparous) are more commonly affected, and each subsequent birth tends to lower risk.
Dietary patterns matter: higher intake of green vegetables, fruit and fish is associated with lower risk, while diets rich in citrus fruits show a marked protective effect. Consumption of food additives and soybean milk has been linked to higher risk. Oral contraceptive use before adulthood may increase later risk, whereas use after adolescence appears protective.
Vitamin D deficiency is common in women with fibroids, and very high serum vitamin E has been noted as a possible risk factor in some groups. Black women have a two‑ to three‑fold higher incidence compared with white women. Overall, lifetime prevalence ranges widely from about 4.5% to 68.6% depending on the population studied.
How fibroids and adenomyosis are diagnosed
- History and examination Periods, pain, pressure, fertility plans; pelvic exam
- Pelvic ultrasound Abdominal or vaginal scan shows fibroids and wall thickness
- MRI if needed Maps fibroids precisely before treatment planning
- Blood tests and biopsy Checks for anaemia and rules out other causes
Diagnosis begins with a detailed history of your periods, pain, pressure symptoms and fertility plans. A pelvic examination allows the doctor to feel the size and shape of the uterus; an enlarged, irregular or tender uterus suggests fibroids or adenomyosis.
The main imaging test is a pelvic ultrasound, performed either on the abdomen or through the vagina, which shows the number, size and location of fibroids and the thickness of the uterine wall in adenomyosis. In some cases an MRI is advised to map the fibroids more precisely before planning treatment.
Blood tests are done to check for anaemia from heavy bleeding and to assess general health before any procedure. An endometrial biopsy may be taken if there is unusual bleeding, to rule out other causes; in studies such biopsies have shown benign histology.
Non‑surgical treatment options and when surgery is considered
If fibroids are small and not causing troublesome symptoms, watchful waiting with regular follow‑up is often appropriate. Medical treatments aim to control bleeding and shrink fibroids temporarily. Gonadotropin‑releasing hormone (GnRH) agonists such as leuprolide acetate and GnRH antagonists such as cetrorelix acetate lower hormone levels and reduce fibroid size.
Selective progesterone receptor modulators like ulipristal acetate and asoprisnil, and the antiprogestin mifepristone, have been studied for bleeding control and volume reduction. In clinical trials, ulipristal acetate controlled uterine bleeding in about 90‑98% of women and reduced median fibroid volume by roughly 45% after one three‑month course, with further reduction after repeated courses.
Hot flashes were less frequent with ulipristal acetate than with leuprolide acetate. Vitamin D and natural compounds such as resveratrol have also been investigated.
Non‑surgical interventional options include uterine artery embolisation, where tiny particles are injected through a catheter to block the blood supply to the fibroids, causing them to shrink. Radiofrequency ablation is another minimally invasive technique.
Surgery is considered when symptoms are severe, medical therapy has not helped or is not suitable, or when fibroids are thought to be affecting fertility. The main surgical options are myomectomy (removing fibroids while keeping the uterus) and hysterectomy (removing the uterus). Myomectomy is generally advised for women who wish to preserve fertility.
The type of myomectomy — open, laparoscopic or hysteroscopic — depends on the size, number and location of the fibroids. Hysterectomy is an option for women who have completed their families and have severe symptoms. Approximately three‑quarters of all fibroid treatments in some settings are hysterectomies.
Your surgeon will discuss which approach fits your situation, the expected hospital stay of one to three nights, and a typical recovery of two to six weeks. New fibroids can develop after myomectomy, especially in women under 40 with many fibroids.
Preparing for fibroid and uterine condition surgery
Do
- Tell surgeon all medicines and supplements
- Bring regular medicines in original packets
Before your operation, your surgeon will ask for a few routine tests.
These usually include:
- Blood counts
- Blood group
- Kidney and liver function
- A test for infections
A chest X-ray and an ECG are common if you are over 40 or have other health problems. An ultrasound or MRI done earlier helps the surgical team plan the procedure.
Tell your surgeon about every medicine you take, including those from a chemist without a prescription, and any supplements. Blood thinners, aspirin, and some painkillers may need to be stopped a few days before surgery. Your surgeon will give you a clear list.
You will be asked not to eat or drink anything for about six hours before the operation. This is because general or spinal anaesthesia is used.
Pack a small bag for a stay of one to three nights. Bring comfortable loose clothes, your regular medicines in their original packets, sanitary pads, and any aids you use such as glasses or a walking stick. An attendant can stay with you in the room.
How fibroid and uterine condition surgery is done
Your surgeon will advise which technique suits you based on the size, number, and location of the fibroids, and whether you wish to keep your uterus. The main options are:
- Laparoscopic myomectomy: The fibroids are removed through small cuts in the abdomen while the uterus is kept. This is often chosen when you want to preserve fertility.
- Hysteroscopic myomectomy: A thin instrument is passed through the vagina and cervix to remove fibroids that bulge into the uterine cavity. No cuts are made on the abdomen.
- Laparoscopic hysterectomy: The uterus is removed through small abdominal cuts. This is considered when the family is complete and symptoms are severe.
- Uterine artery embolisation: An interventional radiologist blocks the blood supply to the fibroids through a tiny puncture in the groin, causing them to shrink.
On the day of surgery, you will be taken to the modular operation theatre. The anaesthetist will give general or spinal anaesthesia. The operation usually takes one to three hours. After the procedure, you will spend some time in the recovery area before moving to your room.
Risks and possible complications of fibroid surgery
All operations carry some risk. In studies, possible complications of myomectomy include infection, bleeding, injury to nearby organs such as the bladder or bowel, and internal scarring called adhesions.
Medical treatments used to shrink fibroids before surgery can cause side effects. In one trial, moderate to severe hot flashes occurred in about 11 percent of women taking 5 mg of ulipristal acetate, 10 percent of those taking 10 mg, and 40 percent of those taking leuprolide acetate.
After surgery, contact the hospital if you develop a fever, severe abdominal pain that is not relieved by the prescribed painkillers, or heavy vaginal bleeding. Your surgical team will discuss the risks that apply to your specific case before you sign the consent form.
Recovery and aftercare after fibroid surgery
Recovery time depends on the type of operation. After an open abdominal myomectomy, full recovery before returning to normal activities can take up to six weeks. After a laparoscopic myomectomy, you may go home the same day or the next day, and recovery at home is about two to four weeks.
If the procedure is done hysteroscopically through the vagina without cuts, full recovery can be just a matter of days.
In the first few days, you will need help at home for cooking, cleaning, and looking after children. Arrange for someone to stay with you for the first one to three days. You will be given pain relief tablets and advised on wound care if you have abdominal cuts. Vaginal spotting or light bleeding is common for a few weeks.
Avoid heavy lifting, strenuous exercise, and sexual intercourse for about four to six weeks, or as your surgeon advises. Most people return to desk work in two to three weeks after keyhole surgery, and four to six weeks after open surgery. Your surgeon will see you for a follow-up visit, usually two to three weeks after discharge.
Call the hospital or visit the 24×7 emergency department if you have a fever above 38°C, increasing pain, heavy bleeding that soaks a pad in an hour, foul-smelling discharge, or difficulty passing urine.
Results of fibroid surgery: symptom relief and recurrence
In studies, most people experience lighter and more regular periods after myomectomy. Medical treatment with ulipristal acetate controlled uterine bleeding in 90 to 98 percent of women in a clinical trial. The same trial showed median fibroid volume shrank by about 45 percent after one three-month course, and by 63 to 72 percent after repeated courses.
However, new fibroids can grow after myomectomy. Younger women under 40 who had many fibroids are at greater risk of developing more fibroids later. Approximately three-quarters of all fibroid treatments in large populations are hysterectomies, which removes the uterus completely and prevents recurrence.
Your surgeon will discuss the likelihood of long-term relief based on your age, the number of fibroids, and the procedure chosen.
Cost and insurance for fibroid surgery in Jaipur
- ₹65,000 Hysteroscopic myomectomy
- ₹75,000 Open myomectomy
- ₹85,000 Laparoscopic myomectomy
- ₹95,000 Total laparoscopic hysterectomy with fibroids
- ₹1,50,000 Robotic myomectomy
The typical price range for fibroid surgery in India is ₹50,000 to ₹2,00,000. The final cost depends on the type of operation, the complexity of your case, the length of stay, and the room category you choose.
For reference, average costs reported in India are around ₹65,000 for hysteroscopic myomectomy, ₹75,000 for open myomectomy, ₹85,000 for laparoscopic myomectomy, ₹95,000 for total laparoscopic hysterectomy with fibroids, and ₹1,50,000 for robotic myomectomy.
Jaipur Hospital is a NABH-accredited multispeciality hospital.
We accept patients under:
- RGHS
- MAA Yojana
- CGHS
- A panel of private insurers and TPAs
If you are covered under one of these schemes, bring your card and any pre-authorisation letter. The hospital's insurance desk can help with the paperwork. For self-pay patients, a deposit is taken at admission and the final bill is settled at discharge. Ask us for an estimate based on your planned procedure.
