

Urology · Jaipur Hospital
Urinary Tract Infections in Jaipur
Repeated urine infections disrupting daily life; we assess, test and give you a clear plan.
- Serving Jaipur since 1991 (35 years)
- NABH accredited
- 24×7 emergency & ICU
- Cashless: RGHS, MAA Yojana, CGHS + 22 insurers
- Consultation length
- 15 to 30 minutes
- Anaesthesia
- Not needed
- Recovery
- Symptom relief in 24 to 48 hours with antibiotics
- Price
- ₹1,500 to ₹5,000 (consultation + basic meds)₹10,000 to ₹25,000 (full recurrent workup)typical range in India; ask us for an estimate
Infections that keep coming back
Urinary tract infections return after treatment
You finish antibiotics, feel better for a few weeks, then the burning, urgency and frequency start again. Each episode means more medicines, missed work and worry about kidney damage.
-
Frequent recurrences
Many women have a repeat infection within six months of the first one.
-
Antibiotic resistance rising
Overuse of antibiotics makes bacteria harder to treat over time.
-
Risk of kidney involvement
Untreated or repeated infections can spread to the kidneys.
-
Daily life disrupted
Pain, urgency and frequent toilet visits affect work, sleep and travel.
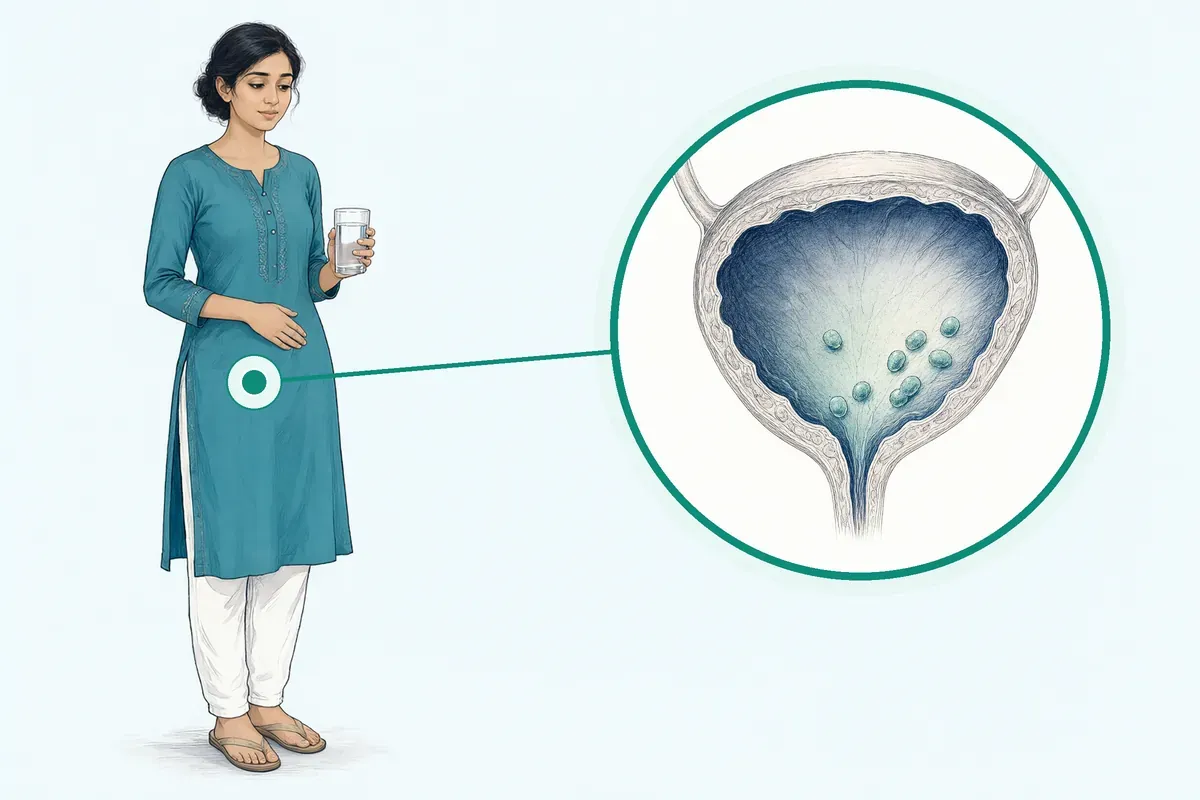
E. coli causes the vast majority of UTIs and uses fimbriae to attach to the urinary lining.
Why Jaipur Hospital
You are tired of the burning, the sudden urges and the fear that the next infection will be worse.
Your care plan
Your first steps with us
- 1 Call or visit OPD for a urology consultation
- 2 Give urine sample for culture and sensitivity testing
- 3 Review results and start targeted antibiotics or prophylaxis
- 4 Attend follow-up visits to confirm the infection is cleared
How we evaluate and treat recurrent UTIs
We take a focused history, order urine culture and sensitivity, and may add imaging or cystoscopy. Treatment is guided by the organism found and local resistance patterns.
-
Urine Culture & Sensitivity
Identifies the exact bacteria and which antibiotics will work against it.
-
Imaging (USG KUB / CT Urogram)
Rules out stones, obstruction or anatomical problems that cause repeat infections.
-
Cystoscopy
A thin scope checks the bladder lining for abnormalities in complex cases.
-
Antibiotic Prophylaxis / Vaccines
Low-dose long-term or post-coital antibiotics; OM-89 vaccine option discussed.
Why patients trust us
- 1991 Serving Jaipur for 35 years
- NABH Accredited hospital
- 24×7 Emergency, ICU and ambulance
- 25 Cashless schemes and insurers
What studies show about recurrent UTI management
-
27 percent of college women had a recurrence within six months
In a study of first-time UTI, over a quarter had a confirmed repeat infection within half a year.
-
53 percent of women over 55 had a recurrence within one year
In primary care, more than half of older women experienced another UTI within twelve months.
-
long-term renal scarring is a common complication
Research notes that kidney scarring can follow certain bacterial infections.
If it is left untreated
Without a proper workup, infections may keep returning, antibiotics may stop working, and bacteria can reach the kidneys causing fever and potential scarring.
Life after a structured UTI plan
Most people find infections become less frequent and easier to manage with a clear protocol.
-
Fewer surprise episodes
A targeted plan reduces the chance of sudden, painful recurrences.
-
Right antibiotic first time
Culture-guided therapy avoids trial-and-error prescribing.
-
Confidence in daily routine
You can travel, work and sleep without constant toilet anxiety.
-
Protect kidney health
Early, correct treatment lowers the risk of upper tract involvement.
Meet the team
Our Urology specialists
Care led by Jaipur Hospital's urology consultants, backed by round-the-clock surgical, diagnostic and critical care support.
Frequently asked questions
Questions patients ask about urinary tract infections
Which problems are assessed under urinary tract infections?
In short
At Jaipur Hospital, the urinary tract infection service assesses acute cystitis, recurrent cystitis, pyelonephritis, asymptomatic bacteriuria, and catheter-associated infections. The team also evaluates underlying causes such as stones, obstruction, anatomical anomalies, and incomplete bladder emptying that can make infections return.
In detail
Recurrent UTI is defined as two or more culture-proven episodes within six months or three within a year.
The workup follows guideline-based steps: a detailed history and pelvic examination where appropriate, urinalysis and urine culture with sensitivity for each symptomatic episode, and imaging such as USG KUB or CT urogram when stones or structural problems are suspected.
Cystoscopy is reserved for complicated or recurrent cases to inspect the bladder lining. The service also screens for risk factors including diabetes, neurogenic bladder, high post-void residual volume, and vaginal atrophy in postmenopausal women. Gram-positive organisms such as Enterococcus and Staphylococcus saprophyticus are considered alongside the predominant uropathogen Escherichia coli.
A common belief
Many people think a UTI is just a bladder infection treated with a short course of antibiotics.
What actually happens
In recurrent cases, the real problem is often an underlying cause such as incomplete emptying, stones, or vaginal atrophy that must be found and managed to stop the cycle.
Your next step at Jaipur Hospital
You can book a 15 to 30 minute outpatient consultation at Jaipur Hospital. Bring any previous culture reports and imaging. The doctor will order the tests needed that day and discuss a plan.
Typical cost for consultation with basic medicines is ₹1,500 to ₹5,000; a full recurrent workup ranges from ₹10,000 to ₹25,000. Call 0141-2551500 to schedule.
How will the doctor decide which tests I need for urinary tract infections?
In short
At Jaipur Hospital, the doctor selects tests based on your symptom pattern, recurrence frequency, risk factors, and prior culture results. A first uncomplicated episode may need only a urine culture. Recurrent or complicated cases typically require culture with sensitivity, imaging such as USG KUB or CT urogram, and sometimes cystoscopy.
In detail
Guidelines recommend urinalysis and urine culture with sensitivity for every symptomatic episode before starting antibiotics. In recurrent UTI, a complete history and pelvic examination (in women) guide further workup.
USG KUB or CT urogram is used to rule out stones, obstruction, or anatomical anomalies when there is suspicion of structural disease, incomplete emptying, or atypical organisms.
Cystoscopy is not routine; it is reserved for complicated or recurrent cases to inspect the bladder for lesions, diverticula, or foreign bodies. Post-void residual volume is measured if incomplete emptying is suspected. Vaginal atrophy is assessed in postmenopausal women. The doctor also reviews local antibiogram patterns to choose empiric therapy while awaiting culture results.
A common belief
Patients often expect every test at the first visit.
What actually happens
Guidelines say imaging and cystoscopy are not routine for a first uncomplicated UTI. They are used when there is a reason — stones, poor emptying, unusual organisms, or repeated infections — to avoid unnecessary cost and radiation.
Your next step at Jaipur Hospital
Your consultation at Jaipur Hospital lasts 15 to 30 minutes. The doctor will order the appropriate tests the same day. Urine culture results are usually available in 24 to 48 hours. Imaging can be done in-house. A full recurrent workup typically costs ₹10,000 to ₹25,000. Call 0141-2551500 to book your visit.
How soon should I expect improvement after the chosen treatment for urinary tract infections?
In short
At Jaipur Hospital, symptom relief from an acute urinary tract infection usually begins within 24 to 48 hours of starting the correct antibiotic. Fever and flank pain from kidney infection may take longer to settle. Prophylaxis measures reduce future episodes over weeks to months.
In detail
For acute cystitis, dysuria, frequency, and urgency typically improve within the first two days of culture-directed therapy. Pyelonephritis requires intravenous antibiotics initially; fever and systemic signs usually resolve over 48 to 72 hours.
If symptoms persist after 48 to 72 hours on appropriate antibiotics, the doctor will reassess for resistance, obstruction, abscess, or alternative diagnoses. Antibiotic prophylaxis shows effect over the first few months — recurrence rates drop when the regimen is followed.
Vaginal oestrogen takes several weeks to restore the vaginal microbiome. Increased water intake, cranberry, methenamine, and the OM-89 vaccine also need consistent use over months to show benefit. The doctor will schedule follow-up based on your response and may repeat urine culture if symptoms do not resolve.
A common belief
Patients often stop antibiotics once they feel better, but the full course is needed to clear the infection and prevent relapse.
What actually happens
Preventive strategies are not instant — they build protection over time. If there is no improvement in 48 hours, the treatment may need adjustment.
Your next step at Jaipur Hospital
After starting treatment, stay in touch with your doctor at Jaipur Hospital. If symptoms do not improve in 48 hours, contact the clinic for review. Prophylaxis follow-up is typically at three and six months. Outpatient visits are 15 to 30 minutes.
When does a fever need testing or hospital assessment for a urinary tract infection?
In short
A fever above 38°C with urinary symptoms suggests the infection may have reached the kidneys. Jaipur Hospital recommends urgent evaluation, as pyelonephritis can cause kidney damage and sepsis if not treated promptly.
In detail
Evidence shows UTIs can ascend from the bladder to the kidneys, causing pyelonephritis with fever, flank pain, nausea, or vomiting. This is a complicated UTI needing blood tests, urine culture, and often imaging like USG KUB or CT urogram.
In studies, delayed treatment of upper UTI increases the risk of irreversible kidney injury and urosepsis. Elderly patients and those with diabetes or urinary obstruction are at higher risk.
A common belief
Some people treat fever at home with paracetamol, hoping the antibiotic will catch up.
What actually happens
But fever with flank pain means the infection has likely reached the kidneys. This needs blood tests, imaging, and often IV antibiotics — not just oral tablets.
Your next step at Jaipur Hospital
Do not wait if you have fever with back pain, chills, or confusion. Go to the 24×7 emergency department at Jaipur Hospital. Initial assessment includes blood work and urine culture. Admission may be needed for intravenous antibiotics.
How can I decide whether to seek advice about recurrent UTI management?
In short
Seek advice if you have had two or more culture-confirmed urinary tract infections within six months, or three within a year. Jaipur Hospital defines recurrent UTI by this standard and offers a full workup including urine culture, imaging and cystoscopy when needed. Frequent infections suggest an underlying cause that should be evaluated.
In detail
Recurrent UTIs are usually reinfections with the same organism persisting in the faecal flora and recolonising the urinary tract. Risk factors include frequent sexual intercourse, postmenopausal vaginal changes, incomplete bladder emptying, and anatomical factors.
Evidence shows that a structured workup — urine culture with each episode, ultrasound or CT urogram to rule out stones or obstruction, and cystoscopy for complicated cases — identifies treatable causes. Nonantibiotic options such as vaginal oestrogen, methenamine hippurate, cranberry, and the OM-89 vaccine may be discussed as prophylaxis.
A common belief
Many people treat each episode separately without looking for the cause.
What actually happens
Guidelines recommend a structured evaluation — cultures, imaging, and sometimes cystoscopy — plus prophylaxis options like vaginal oestrogen or methenamine.
Your next step at Jaipur Hospital
Keep a record of your symptoms, urine culture reports, and antibiotics taken. If you meet the recurrence criteria, schedule a consultation. The workup is outpatient and typically completed in one to two visits.
Which urinary symptoms need urgent assessment?
In short
Urgent assessment is needed for high fever with shaking chills, severe flank or back pain, nausea and vomiting, inability to pass urine, visible blood in urine with clots, or new confusion in an older adult. Jaipur Hospital provides 24×7 emergency care for these red-flag symptoms, which may indicate pyelonephritis, obstruction, sepsis, or urinary retention requiring immediate intervention.
In detail
Fever and flank pain suggest upper tract infection (pyelonephritis) which can cause renal scarring if delayed. Inability to void may indicate obstruction from a stone, stricture, or prostate enlargement. Gross haematuria with clots can signal a bleeding tumour or severe infection.
In older adults, new confusion or lethargy may be the only sign of severe infection or sepsis. Evidence shows that prompt culture-guided antibiotics and drainage of obstruction improve outcomes. The emergency department can start IV antibiotics, obtain imaging, and involve urology without delay.
A common belief
Burning and frequency alone can wait for an OPD visit.
What actually happens
But fever plus flank pain means kidney infection; not passing urine means obstruction; confusion in the elderly can mean sepsis. These need immediate IV antibiotics and imaging.
Your next step at Jaipur Hospital
Do not wait for routine OPD hours if you have any of these symptoms. Go to the emergency department or call the ambulance service. Early treatment prevents complications.
Which symptoms should prompt me to see a specialist?
In short
You should see a specialist at Jaipur Hospital if you have burning or pain while passing urine, frequent urge to urinate, blood in the urine, lower abdominal discomfort, or fever with flank pain suggesting kidney involvement. Recurrent episodes — two or more in six months — also warrant a specialist review.
In detail
Guideline-based practice defines recurrent UTI as two culture-proven episodes within six months or three within a year. Symptoms such as dysuria, frequency, urgency, suprapubic pain, and haematuria point to cystitis. Fever, chills, flank pain, nausea, or vomiting suggest pyelonephritis, which is more serious.
In older adults, confusion or general decline may be the only sign. Postmenopausal women with incontinence, cystocele, or post-void residual volume above 50 mL have a higher risk of recurrence. A previous UTI, recent sexual activity, diabetes, and structural abnormalities are established risk factors. The specialist will document inflammation (pyuria) and obtain a urine culture with sensitivity before starting treatment.
A common belief
People often wait until they have had several episodes before seeking help.
What actually happens
Early specialist review can identify correctable causes such as incomplete bladder emptying or vaginal atrophy, and it ensures the right antibiotic is chosen from the first culture, reducing resistance risk.
Your next step at Jaipur Hospital
Visit the urology OPD at Jaipur Hospital for a 15 to 30 minute consultation. Carry any prior culture reports. The doctor will take a focused history, examine you if needed, and order a urine culture and basic imaging if indicated. Typical consultation cost with basic medicines is ₹1,500 to ₹5,000.
How will the results change my care plan for urinary tract infections?
In short
At Jaipur Hospital, urine culture and sensitivity results directly guide antibiotic choice, ensuring the drug matches the organism. Imaging findings such as stones, obstruction, or high post-void residual may lead to surgical correction or bladder drainage. Cystoscopy findings can reveal lesions or anatomical issues needing specific treatment. Vaginal atrophy in postmenopausal women may prompt local oestrogen therapy.
In detail
Culture-directed therapy is the standard: the antibiotic is narrowed once sensitivities are known, typically within 24 to 48 hours.
If the organism is resistant to first-line oral agents (nitrofurantoin, trimethoprim-sulfamethoxazole, fosfomycin), parenteral antibiotics may be used for a short course, generally no longer than seven days. A stone causing obstruction with infection requires urgent drainage (stent or nephrostomy) plus antibiotics.
High post-void residual may need catheterisation or surgical intervention. Vaginal oestrogen reduces recurrence in postmenopausal women without contraindications. Antibiotic prophylaxis — low-dose long-term or post-coital — may be offered after discussing risks and benefits. Cranberry and methenamine hippurate are non-antibiotic options. The OM-89 vaccine is an immunostimulant option. Asymptomatic bacteriuria is not treated except in pregnancy or before urological procedures.
A common belief
A common mistake is continuing the same antibiotic without checking the culture.
What actually happens
If the bacteria are resistant, the infection persists and resistance worsens. Results also reveal whether the problem is just the bacteria or something structural that antibiotics alone cannot fix.
Your next step at Jaipur Hospital
After your tests, the doctor at Jaipur Hospital will review results with you and adjust the plan. Most antibiotic changes happen within 48 hours of culture. If a procedure is needed, the team will explain timing and preparation. Follow-up is outpatient.
What should I do if urinary tract infection symptoms persist or worsen?
In short
If your urinary tract infection symptoms persist or worsen, contact Jaipur Hospital promptly for a repeat urine culture and clinical review. Symptom relief usually occurs within 24 to 48 hours after starting appropriate antibiotics. Persistent burning, frequency, blood in urine, or new fever may indicate resistant bacteria, incomplete treatment, or an underlying issue such as a stone or obstruction that needs further evaluation.
In detail
Guidelines recommend repeating urine cultures when symptoms continue after antimicrobial therapy to guide further management. A positive culture with greater than 102 colony-forming units per mL confirms infection in symptomatic patients.
Resistant organisms may require culture-directed parenteral antibiotics for a short course, generally no longer than seven days. If cultures are negative but symptoms persist, the clinician should evaluate for alternative causes such as interstitial cystitis, urethral syndrome, or pelvic floor dysfunction.
Imaging with USG KUB or CT urogram and cystoscopy are reserved for recurrent or complicated cases to rule out stones, anatomical anomalies, or bladder pathology.
A common belief
Many people assume the antibiotic just needs more time, but guidelines show that ongoing symptoms often mean resistant bacteria or another cause like a stone.
What actually happens
Continuing the same drug without a new culture can delay proper treatment.
Your next step at Jaipur Hospital
Do not wait more than 48 hours after starting antibiotics if you feel no improvement or if fever, flank pain, or vomiting develop. Bring any recent reports to the urology OPD for a 15 to 30 minute consultation. The surgeon will review culture results, adjust antibiotics if needed, and discuss whether imaging or cystoscopy is indicated.
Which tests are useful at different stages of a urinary tract infection illness?
In short
At Jaipur Hospital, the test plan depends on whether this is a first episode, a recurrence, or a complicated case. For a first symptomatic episode, a urine culture and sensitivity is the standard test. For recurrent infections, a full workup adds imaging and sometimes cystoscopy. Your surgeon selects tests based on your history and examination findings.
In detail
Guidelines recommend urinalysis and urine culture with each symptomatic episode before starting antibiotics. A clean-catch specimen showing greater than 10 to the power of 2 colony-forming units per millilitre of a uropathogen confirms infection.
For recurrent UTIs, defined as two episodes in six months or three in a year, the workup includes USG KUB or CT urogram to rule out stones, obstruction, or anatomical anomalies. Cystoscopy is reserved for recurrent or complicated cases to inspect the bladder lining.
Postmenopausal women may need a pelvic examination and assessment of post-void residual volume. Asymptomatic bacteriuria does not need treatment or routine surveillance cultures. Blood tests such as creatinine and blood sugar are added if kidney involvement or diabetes is suspected.
A common belief
People often repeat the same basic test.
What actually happens
But guidelines say each symptomatic episode needs a fresh culture before antibiotics. Recurrent UTIs need a structured workup: imaging for stones or obstruction, cystoscopy for bladder inspection, and post-void residual checks in older women. Asymptomatic bacteriuria does not need routine testing or treatment.
Your next step at Jaipur Hospital
For a new episode, visit the OPD for a urine culture before taking antibiotics. Results guide targeted therapy in 24 to 48 hours. If you have had two or more infections in six months, book a recurrent UTI workup consultation at Jaipur Hospital.
The full workup typically costs ₹10,000 to ₹25,000 and is completed over one to two visits. Your surgeon will explain which tests you need and when. Call 0141-2551500 to schedule.
FAQ library
Questions and answers about urinary tract infections
When you contact us
Get your UTI assessment plan
Contact Jaipur Hospital for a urology consultation, in-house tests and a clear, cost-estimated plan with cashless scheme support.
- A consultation with a urologist in the OPD
- Your scans and reports reviewed, with tests done in-house if you need them (laboratory, X-ray and imaging)
- Your options explained in plain words, including whether you need surgery at all
- A cost estimate before you decide
- Help with cashless treatment under RGHS, MAA Yojana, CGHS and empanelled insurers and TPAs
- Follow-up visits after your treatment
Overview
Urinary Tract Infections: what to know
What a urinary tract infection is and how it happens
- Bacteria enter urethra Often from skin or rectum
- Bladder infection Called cystitis
- Kidney infection Called pyelonephritis
A urinary tract infection (UTI) is an infection in any part of the urinary system, which includes the bladder, the urethra and the kidneys. Most infections involve the lower urinary tract — the bladder and the urethra.
When bacteria, often from the skin or rectum, enter the urethra, they can travel up to the bladder and cause an infection called cystitis. If the infection moves further up to the kidneys, it is called pyelonephritis, which is less common but more serious.
The most common cause is a bacterium called Escherichia coli, or E. coli, which lives in the bowel. In community-acquired infections, E. coli accounts for the vast majority of cases. These bacteria have special features, such as fimbriae, that help them stick to the lining of the urinary tract and form biofilms, making them harder to clear.
Other bacteria such as Klebsiella, Pseudomonas, Proteus and Staphylococcus saprophyticus can also cause UTIs, especially when there are risk factors like a catheter, diabetes or structural problems.
Sometimes bacteria are found in the urine but cause no symptoms. This is called asymptomatic bacteriuria and usually does not need treatment. In fact, these harmless bacteria may help prevent infection by more harmful types. A UTI is diagnosed only when there are symptoms along with bacteria in the urine.
Symptoms of UTI and warning signs that need urgent care the same day
- Fever and chills
- Back or side pain
- Nausea and vomiting
- Confusion in older adults
Common symptoms of a bladder infection include:
- Pain or a burning feeling when you pass urine
- Needing to pass urine more often than usual
- Seeing blood in the urine
You may also feel pressure or discomfort in the lower abdomen.
A kidney infection is more serious. Warning signs that need medical attention the same day include fever, chills, pain in the back or side below the ribs, nausea and vomiting. In infants and young children, fever may be the only sign of a UTI.
If you notice any of these kidney infection symptoms, contact your doctor or go to the emergency department without delay.
In older adults, confusion or a sudden change in behaviour can sometimes be the only clue. If you are unsure, it is safer to get checked the same day.
Causes and who is at higher risk of urinary tract infection
UTIs happen when bacteria enter the urinary tract. The shortest route is through the urethra. Because women have a shorter urethra that is closer to the rectum, they get UTIs more often than men. Sexual activity can move bacteria toward the urethra, and frequent intercourse is the strongest predictor of recurrent UTIs in young women.
Other factors that raise the risk include:
- A previous UTI
- Changes in vaginal bacteria, such as after menopause or with spermicide use
- Pregnancy
- Older age or very young age
- Structural problems like an enlarged prostate, kidney stones or a narrowing of the urethra
- Poor hygiene, especially in children learning to use the toilet
- Diabetes, which can affect immunity and bladder emptying
- Neurologic conditions or a spinal cord injury that make it hard to empty the bladder fully
- A urinary catheter, either short-term or long-term
- In postmenopausal women, incomplete bladder emptying (more than about 50 mL left after passing urine) is an independent risk factor for recurrence.
Recurrent UTI is defined as two or more culture-proven episodes in six months, or three or more in a year. Most recurrences are reinfections — the same bacteria return from the bowel after the first infection is cleared. A smaller number are relapses, where the original bacteria were not fully eradicated.
How urinary tract infection is diagnosed: examination and tests
Your doctor will ask about your symptoms and medical history. In women with recurrent UTIs, a pelvic examination may be done to check for signs of incomplete bladder emptying or vaginal changes.
The main test is a urine culture and sensitivity. A clean-catch midstream sample is sent to the laboratory to grow the bacteria and test which antibiotics will work. In symptomatic patients, a count of more than 10² colony-forming units per mL of a known uropathogen is considered positive. If the first sample looks contaminated, a repeat sample or a catheterised specimen may be taken.
For a first or simple UTI, imaging and cystoscopy are not routinely needed. If you have recurrent or complicated infections, your surgeon may advise an ultrasound of the kidneys and bladder (USG KUB) or a CT urogram to look for stones, blockages or anatomical differences.
Cystoscopy — a thin camera passed into the bladder — is reserved for cases where the cause is unclear after imaging, or when there are persistent symptoms despite negative cultures.
Asymptomatic bacteriuria (bacteria in the urine without symptoms) is not treated in most people. Surveillance urine cultures when you have no symptoms are also not recommended.
Treatment options without surgery for urinary tract infection, and when surgery is advised
Do
- Pass urine after sexual activity
- Stay well hydrated
- Take showers instead of baths
- Wipe from front to back
Most UTIs are treated with a short course of oral antibiotics chosen according to the urine culture result and local resistance patterns.
First-line options often include:
- Nitrofurantoin
- Trimethoprim-sulfamethoxazole
- Fosfomycin
The course is usually no longer than seven days for an acute episode. If the bacteria are resistant to oral antibiotics, a short course of intravenous antibiotics may be given in hospital. Symptom relief typically begins within 24 to 48 hours of starting the right antibiotic.
For recurrent UTIs, several non-surgical strategies can reduce future episodes:
- Antibiotic prophylaxis: a low daily dose, a dose after intercourse, or a short course started by you at the first symptom (self-start therapy).
- Vaginal oestrogen cream or pessary for postmenopausal women, if there is no medical reason to avoid it.
- Cranberry products may help some women.
- Methenamine hippurate is an option that works by making the urine acidic.
- Drinking more water — aiming for at least 1.5 litres a day — can help if your current intake is low.
- Behavioural steps: pass urine after sexual activity, stay well hydrated, take showers instead of baths, avoid douches and sprays in the genital area, and wipe from front to back.
Non-antibiotic options such as probiotics, D-mannose and vaccines (for example OM-89) have been studied, but high-level evidence is still limited and they are not yet standard recommendations.
Surgery is not a treatment for the infection itself. It is advised only when an underlying structural problem is found — such as a stone causing obstruction, a stricture, or an anatomical abnormality that prevents the bladder from emptying completely. Correcting that problem can stop infections from coming back. Your surgeon will discuss whether a procedure is needed based on the imaging and cystoscopy findings.
Preparing for recurrent UTI workup at Jaipur Hospital
Your first visit usually takes 15 to 30 minutes.
Bring any earlier:
- Urine culture reports
- Imaging films
- A list of antibiotics you have taken in the past six months
Tell your surgeon about every medicine you use, including:
- Blood thinners
- Diabetes tablets
- Any supplements
No fasting is needed for the consultation or for giving a urine sample. If a cystoscopy is planned later, you will be asked to stop blood thinners a few days before and to keep the bladder comfortably full on the day of the test. Wear loose clothing and bring an attendant if you wish.
How recurrent UTI workup and treatment are done at Jaipur Hospital
- Clean-catch urine culture Identifies organism and antibiotic sensitivity
- Imaging if infections return USG KUB or CT urogram
- Cystoscopy for complex cases Inspects bladder lining directly
- Culture-guided treatment plan Antibiotics chosen by sensitivity results
The workup starts with a clean-catch urine sample for culture and sensitivity. This identifies the organism and shows which antibiotics will work. If infections keep coming back, your surgeon may order an ultrasound of the kidneys, ureters and bladder (USG KUB) or a CT urogram to look for stones, blockage, or anatomical differences.
Cystoscopy is offered for recurrent or complicated cases to inspect the bladder lining directly. Based on the results, your surgeon will choose a culture-guided antibiotic course.
For prevention, options include:
- Low-dose daily antibiotic prophylaxis
- A single post-coital dose
- Methenamine hippurate
- Vaginal oestrogen for postmenopausal women
- The OM-89 vaccine
Cranberry products may be discussed as an option, though evidence varies. Your surgeon will explain which approach fits your pattern of infections.
Risks and possible complications of recurrent UTI investigations and prophylaxis
- Cystoscopy
- Temporary burning, slight bleeding, brief UTI
- Antibiotic prophylaxis
- Nausea, rash, yeast infection, diarrhoea, resistant bacteria
- Methenamine hippurate and vaginal oestrogen
- Generally well tolerated
- OM-89 vaccine
- Mainly mild stomach upset reported
Urine culture and imaging are non-invasive and carry no significant risk. Cystoscopy can cause temporary burning on passing urine, slight bleeding, or a brief urinary tract infection; these usually settle in a day or two. Antibiotic prophylaxis may lead to nausea, rash, yeast infection, or diarrhoea in some people.
Long-term use can encourage resistant bacteria, which is why the choice of drug and duration are reviewed regularly. Methenamine hippurate and vaginal oestrogen are generally well tolerated. The OM-89 vaccine is given as a course of oral capsules; studies report mainly mild stomach upset. If you develop fever, flank pain, or worsening symptoms after any test or new medicine, contact the hospital.
Recovery and aftercare after recurrent UTI treatment
Symptom relief typically begins within 24 to 48 hours of starting the right antibiotic. Finish the full course even if you feel better. Drink plenty of water and urinate after sexual activity. If you are on daily prophylaxis, take the dose at bedtime. For post-coital prophylaxis, take the single dose within two hours of intercourse.
Vaginal oestrogen is used as a cream or pessary, usually nightly for two weeks then twice weekly. The OM-89 vaccine schedule is one capsule daily for three months. Your surgeon will review you at four to six weeks to check symptom control and repeat a urine culture if needed. No routine test of heal is done when you have no symptoms.
Call the hospital if:
- Fever returns
- Pain moves to the back
- You see blood in the urine
Results of recurrent UTI workup and prophylaxis
- 27 percent College women, six months
- 36 percent Younger women, one year
In studies, culture-guided therapy clears the current infection in the large majority of patients. Antibiotic prophylaxis reduces the number of episodes per year compared with no prophylaxis. In one large trial of college women with a first UTI, 27 percent had at least one culture-confirmed recurrence within six months without prophylaxis.
In primary care, 53 percent of women older than 55 years and 36 percent of younger women had a recurrence within one year. Vaginal oestrogen lowers recurrence rates in postmenopausal women. Methenamine hippurate and cranberry products show benefit in some trials but not all. The OM-89 vaccine has shown promise in early studies; larger human trials are still needed. Your own results depend on the underlying cause, anatomy, and how closely the prevention plan is followed.
Cost and insurance for recurrent UTI care at Jaipur Hospital, Jaipur
A single consultation with basic medicines typically costs ₹1,500 to ₹5,000. A full recurrent workup including cultures, imaging and cystoscopy usually falls between ₹10,000 and ₹25,000. The final amount depends on the number of tests, the type of imaging, whether cystoscopy is needed, and the length of any prophylaxis prescription.
Jaipur Hospital accepts:
- RGHS
- MAA Yojana
- CGHS
- A panel of private insurers and TPAs
The in-house pharmacy and diagnostic laboratory mean all tests and medicines are available on site. Ask at the reception for an estimate before you start the workup.
